The Ulutas Medical Journal · ISSN 2149-0430 (印刷版), 2149-388X (在线版) · https://www.ulutasmedicaljournal.com/?mno=185234
病例报告 · 开放获取
肠内膜胃切除术的胃内膜瘘-延迟并发症,案例报告
标题、摘要和全文为机器翻译。 英文原文
- Kadirli State Hospital,Department of General Surgery,Osmaniye ROR
- Kadirli State Hospital,Department of Neurology,Osmaniye ROR
- Kadirli State Hospital,Department Radiology,Osmaniye ROR
- 开放获取
- CC BY-NC 4.0
- ORCID
- 资助
- 伦理批准
- 数据可用性
摘要
背景:皮内膜胃切除管是长期喂养病人的一种既定、有效和相对安全的技术。 然而,胃内膜瘘是PEG的主要并发症。 案例介绍:一名患有脑部严重梗塞的82岁妇女被平稳地放置PEG管进行肠内喂养。 几个月后,在每次PEG管进食后几分钟内发展出短暂的腹泻. 另一个胃切除管被手术放置,瘘管随后也被切除. 术后课程很平稳。 结论:当患者在输卵管喂食后突然出现无法解释的腹泻时,必须将胃凝胶性瘘管作为PEG管放置的复杂因素.
关键词
全文
全文为机器翻译;正式发表的版本为英文原文。 英文原文
导言
皮肤内分泌胃切除术通常用于长期喂养无法通过口腔喂养的患者. 自1980年Gauderer和同事推出PEG以来,该程序已成为一种得到良好接受的安全技术。 (1)总的来说,复杂率很低。 PEG的大多数并发症都被认为是轻微的,包括伤口感染、管子消散和渗漏。 (2–4)然而,胃切皮瘘是PEG的主要并发症。
肠道穿透结肠而形成的胃凝皮瘘管病,或是在PEG过程中无意中刺穿横肠,或随着时间的推移侵蚀到邻近肠道。 据报告,这种并发症是罕见的;Pitsinis等人进行的一项研究表明,这种并发症的发生率在成人中为0.5%。 (5). 患有这种并发症的病人可以长期保持不出现典型症状,已报告有几例长期无症状的病例 (6, 7)因此,提高认识有助于避免这种复杂情况,高指数的怀疑可以确保及早诊断。 在此,我们报告一个案例,即PEG在经过长时间的无症状期后插入后出现这种复杂情况。
案件报告
一名患有脑部严重梗塞的82岁妇女接受了平稳的PEG管插插,用于肠内喂食。 在接下来的几个月里,患者在肠管喂食方面没有困难,直到更换PEG管. 瞬间腹泻突然发作,在每次PEG输卵管进食后几分钟内就会出现。 管子周围的皮肤被棕黄色的流体激起。 在使用上部内膜检查管位时,没有看到胃部内部的保险杠。 从PEG管注入胃草芬的放射图像显示,在转盘结肠中,带有结肠填充胃草芬的管尖.
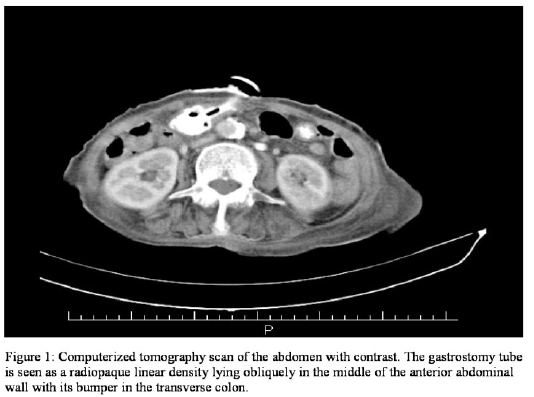
计算成型的成像仪确认位置错位,将保险杠在横肠的位置定位(图1) (中文(简体) ). 没有对比材料进入腹腔. 进行了拉帕罗切除术,以关闭瘘管,并取代胃切除术(图2) (中文(简体) ). 术后航线平稳,她通过新的胃切除管进食没有进一步困难.
讨论情况
近皮内分泌胃切除管是一种成熟、有效、相对安全的长期喂养病人的技术。 一般来说,复杂率较低,PEG管向原位于胃部的结肠中迁移是一种极为罕见的复杂情况,一般在插入后数日到数月内发生。 (8, 9)在前一次腹部手术的患者中也发现了此病。 (10)妇科呕吐症和促发性腹泻是胃内皮炎最常见的两个症状,都存在于患者体内。 本案中不寻常的是,在PEG插入后长时间出现胃阴道瘘,而且以前没有做过手术。
胃肠道瘘的确切机理并不广为人知。 然而,最可信的理论是将结肠,通常是横肠,介于前腹壁和胃壁之间. (11, 12).导针从皮肤传入结肠,然后进入胃部. PEG管跟随针头通过胃向后退,先是穿透结肠,然后离开皮肤. 这一假设得到腹部计算成像扫描的支持(图1) (中文(简体) ).
已公布了胃肠道剪切瘘管的不手术管理战略,包括纤维素胶水、非类固醇抗炎药物、母体营养和静脉注射丙胺 (13–17)然而,这种非手术管理可能并非所有患者都成功。 对胃病瘘管病进行彻底管理需要外科手术。 我们为这个案子做了手术
利用转光和手指压力作为针刺地点定位指南的技术对于防止这种复杂情况很有用。 超声波或CT的引导可以有选择地使用,但可能好处有限. FOUTCH等人建议,如果在注射器内出现气泡之前,在胃部的口腔内窥视针头时,可以使用充满盐水的呼吸注射器来辨别皮肤和胃之间的结肠。 (10)。 。 。
结论
最后,当患者在PEG管喂食后突然出现不明原因的痢疾时,胃内膜瘘必须作为PEG管插管的并发症,并应当通过CT确认诊断结果。 症状的延迟发作或间歇性发生并不排除胃膜瘘。 为了避免这种复杂情况,高风险群体的病人必须在PEG之前进行仔细评估。
声明
- 作者贡献(CRediT)
- 所有作者对全部 14 项 CRediT 角色贡献均等(Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing)。
- 资助
-
Funding information was not reported in the published version of this article.
- 利益冲突
- A conflict of interest statement was not reported in the published version of this article.
- 伦理批准
- Ethics approval details were not reported in the published version of this article.
- 数据可用性
- A data availability statement was not reported in the published version of this article.
参考文献 (17)
17 条参考文献中有 11 条已链接 DOI。
- Gauderer MWL. Percutaneous endoscopic gastrostomy 20 years later: historical perspective. J Pediatr Surg 2001;36:217-9. DOI Crossref PubMed Google Scholar
- Sherwin P, Schrag S, Sharma S, et al. Complications related to percutaneous endoscopic gastrostomy (PEG) tubes. A comprehensive clinical review. J Gastrointestin Liver Dis 2007;16:407–18. PubMed Google Scholar
- Sasaki T, Fukumori D, Sakai K, Sato M, Ohmori H, Yamamoto F. The safety and feasibility of percutaneous endoscopic gastrostomy placement. Hepatogastroenterology 2004;51:1062–5. PubMed Google Scholar
- Friedmann R, Feldman H, Sonnenblick M. Misplacement of percutaneously inserted gastrostomy tube into the colon: report of 6 cases and review of the literature. JPEN J Parenter Enteral Nutr 2007;31:469 –76. DOI Crossref PubMed Google Scholar
- Pitsinis V, Roberts P. Gastrocolic fistula as a complication of percutaneous endoscopic gastrostomy. Eur J Clin Nutr 2003;57:876-8. DOI Crossref PubMed Google Scholar
- Sarsu SB, Karapur A. Ileal Perforation Caused by Typhoid Fever. Ulutas Med J. 2015; 1(3): 86-89. DOI Crossref PubMed Google Scholar
- Marcy PY, Magne N, Lacroix J, Bailet C. Late presentation of gastrocolic fistula after percutaneous fluoroscopic gastrostomy. JBR-BTR 2004;87:17-20. PubMed Google Scholar
- Huang SY, Levine MS, Raper SE. Gastrocolic fistula with migration of feeding tube into transverse colon as a complication of percutaneous endoscopic gastrostomy. AJR Am J Roentgenol 2005;184:S65-S66. DOI Crossref PubMed Google Scholar
- Lenzen H, Weismuller T, Bredt M, Bahr M. Education and imaging. Gastrointestinal: PEG feeding tube migration into colon;late manifestation. J Gastroenterol Hepatol 2012;27: 1254. DOI Crossref PubMed Google Scholar
- Foutch PG et al. Percutaneous endoscopic gastrostomy in patients with prior abdominal surgery: virtues of the safe tract. Am J Gastroenterol 1988;83:147-150. PubMed Google Scholar
- Roozrokh HC, Ripepi A, Stahlfeld K. Gastrocolocutaneous Fistula as a complication of peg tube placement. Surg Endosc. 2002;16:538–9. DOI Crossref PubMed Google Scholar
- Minocha A, Rupp TH, Jaggers TLSilent cologastrocutaneous fistula as complication of percutaneous endoscopic gastrostomy. Am J Gastroenterol 1994;89:2243-2244. PubMed Google Scholar
- Rots WI, Mokoena T. Successful endoscopic closure of a benign gastrocolonic fistula using human fibrin sealant through gastroscopic approach: a case report and review of the literature. Eur J GastroenterolHepatol 2003;15:1351-6. DOI Crossref PubMed Google Scholar
- Shand A, Reading S, Ewing J, et al. Palliation of a malignant gastrocolic fistula by endoscopic human fibrin sealant injection. Eur J GastroenterolHepatol 1997;9:1009-11. DOI Crossref PubMed Google Scholar
- Tan CC, Guan R et al. Closure of a benign gastrocolic fistula on medical management. Singapore Med J 1994;35:423-5. PubMed Google Scholar
- Thyssen EP, Weinstock LB, Balfe DM, et al. Medical treatment of benign gastrocolic fistula. Ann Intern Med 1993; 118:433-5. DOI Crossref PubMed Google Scholar
- Ahamed F, Chandrappa N, Abdallah EM. A comparative study of diagnosis methods for detection of Helicobacter pylori in gastro-duodenal diseases in Human. Ulutas Med J. 2015; 1(3): 64-67. Cite? DOI Crossref PubMed Google Scholar
阅读全文
在此打开 PDF
正在加载 PDF…
若 PDF 未在此显示,请使用上方的下载按钮。
如何引用本文
Sarici IS, Kala F, Kara G, Eskut N, Gundogdu E. Gastrocolocutaneous Fistula-Delayed complication of Percutaneous Endoscopic Gastrostomy, Case report. Ulutas Med J. 2015;1(4):116-118. doi:10.5455/umj.20150417122313
Sarici, I. S., Kala, F., Kara, G., Eskut, N., & Gundogdu, E. (2015). Gastrocolocutaneous Fistula-Delayed complication of Percutaneous Endoscopic Gastrostomy, Case report. The Ulutas Medical Journal, 1(4), 116–118. https://doi.org/10.5455/umj.20150417122313
Sarici, I.S. et al. (2015) 'Gastrocolocutaneous Fistula-Delayed complication of Percutaneous Endoscopic Gastrostomy, Case report', The Ulutas Medical Journal, 1(4), pp. 116–118. doi: 10.5455/umj.20150417122313.