The Ulutas Medical Journal · ISSN 2149-0430 (مطبوع), 2149-388X (إلكتروني) · https://www.ulutasmedicaljournal.com/?mno=55300
تحليل تلوي · وصول مفتوح
Iclaprim Versus Vancomycin for the Treatment of Acute Bacterial Skin and Skin Structure Infection: A Systematic Review and Meta-analysis of Randomized Controlled Trials
ترجمة آلية للعنوان والملخص والنص الكامل. الأصل الإنجليزي
- Pharmaceutical Sciences and Medical Technology, Putian University, Putian, China ROR
- Intensive Care Medicine, Chi Mei Medical Center, Liouying, Taiwan ROR
- Yijia Pharmacy, Tainan, Taiwan
- School of Management, Putian University, Putian, China ROR
- Orthopedic Surgery, Tung’s Taichung MetroHarbor Hospital, Wuqi District, Taichung City, Taiwan ROR
الملخص
وقيّم هذا التحليل المميت فعالية وسلامة النيكلبريم مقارنة بمعاملات الفانكومسين في معالجة الجلد البكتيري الحاد والإصابة بهيكل الجلد. ولم تُدرَج سوى المحاكمات العشوائية الخاضعة للمراقبة التي تقارن أثر النسيج مع الفانكومسين على المرضى البالغين المصابين بمرض الإيدز. A total of 3 RCTs involving 1260 adult patients with ABSSSIs were enrolled. وكان لدى إيكلابريم معدل استجابة سريرية غير أدنى بالمقارنة مع فانكومسين. ولوحظ اتجاه مماثل في المجموعات الفرعية التالية: الاختراقات الكبيرة، والتهاب الخلايا/الريبا، والإصابة بالجرحى، والإصابات بالجروح، والإصابات الناجمة عن الالتهاب المغناطيسي، والإصابات الناجمة عن الالتهاب المغناطيسي في ستريبتوكوس. Finally, no differences were observed between iclaprim and vancomycin regarding the risks of any AE, drug-related AE, severe AE, discontinuation of study drug due to AE, and mortality. In conclusion, iclaprim exhibits non-inferior efficacy compared with vancomycin in the treatment of ABSSSI. وبالإضافة إلى ذلك، تم التسامح عموما مع مشروع " إكلامبريم " على أنه " فانكومسين " .
الكلمات المفتاحية
النص الكامل
ترجمة آلية للنص الكامل؛ النسخة المنشورة الرسمية هي الأصل الإنجليزي. الأصل الإنجليزي
مقدمة
The incidence of acute bacterial skin and skin structure infection (ABSSSI) has gradually increased since 2000 and has become one of the most common types of infections (1–4)إدارة مضادات حيوية مناسبة هي أساسية في معالجة حالات الإصابة بفيروس نقص المناعة البشرية/متلازمة نقص المناعة المكتسب (الإيدز)، التي تشمل التهاب الخلايا/الريبا، والاختراقات القاطعة الرئيسية، والإصابة بالإصابة بالجرح؛ ومن ثم، فإن هذا الكيان السريري هو أيضا سبب مشترك للوصفات المضادة للأوبئة في جميع أنحاء العالم (5, 6)- كما هو الحال بالنسبة لأنواع أخرى من الأمراض، مثل الالتهاب الرئوي، والعدوى داخل البطن، والالتهاب البولي، والبكتيريا، أدى ظهور الكائنات الحية المتعددة المقاومة للأدوية إلى الحد إلى حد كبير من اختيار العلاج المضاد للفيروسات العكوسة وأثر سلبا على نتائج المرضى المصابين بمبيدات الآفات. Among ABSSSIs, methicillin-resistant Staphylo coccus aureus (MRSA) is the most notorious MDRO (7, 8)- أوصت جمعية الأمراض المعدية في أمريكا بتغطية إمبراطورية لوكالة أطباء بلا حدود من أجل التطهير من مرض الإيدز والعدوى. (9)In addition to vancomycin, daptomycin, and linezolid, which are conventional intravenous antibiotics for treating MRSA infection, several novel antibiotics with the anti-MRSA activity, including omadacycline, ceftaroline fosamil, delafloxacin, oritavancin, and telavancin, have been approved by the FDA for treatments (10–14)(ب) يمكن للمؤسسة، وهي مادة مضادة حيوية من نوع ديامينوبيريميدين، أن تثبط الخناق البكتيرية للهيدروفولات، ولا تعرض سوى القليل إلى عدم إعاقة الانزيم البشري بتركيزات عالية، وهو ما يتطلب ما لا يقل عن 4 أوامر بحجم أعلى مما هو ضروري لإبطال مفعول سداسي كلور حلقي الهكتار المكتري (15, 16)وقد بيّن العديد من الدراسات المتعلقة بالفيروسات أن الكيلابريين يُظهر نشاطاً قوياً ضد مسببات الأمراض، بما في ذلك مسببات الأشعة فوق البنفسجية (+) (17, 18) غير أن فعالية وسلامة هذه العقاقير الجديدة لم يُبلغ عنها إلا في دراسات سريرية محدودة، في حين أن الخبرة في الممارسة السريرية في العالم الحقيقي لا تزال ضئيلة. (19–22)وعلاوة على ذلك، لا يزال من غير الواضح ما إذا كانت الكفاءة السريرية وخطر وقوع أحداث ضارة (AEs) في النسيج (AEs) لا يقلان عن تلك التي يستخدمها عادة وكلاء مكافحة العلاقة بين الجنسين مثل الفانكومسين. ولذلك، أجرينا هذا التحليل الدقيق للمحاكمات المراقَبة عشوائياً من أجل المقارنة بين نظام " إيلامبريم " و " فانكومسين " في معالجة " ABSSSIs " .
المواد والأساليب
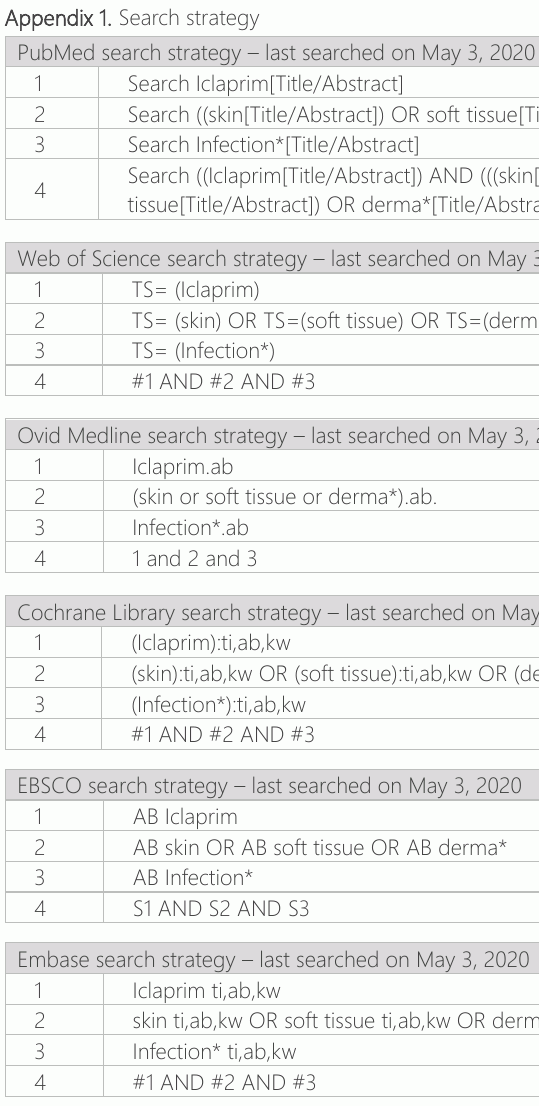
تم تحديد جميع الدراسات المرشحة في البداية بإجراء استعراض منهجي لقواعد البيانات، وهي: PubMed, Web of Science, EBSCO, Cochrane Library, Ovid Medline, and Embase database until May 3, 2020, by using following terms: "iclaprim, " " skin, " " " , "derma, " and "infection " . ولم تُدرَج إلا سلاسل RCTs التي قارنت الكفاءة السريرية وخطر التعرض للإصابة بمرض الكتلبري والفانكومسين لعلاج المرضى البالغين (متوسط العمر 18 سنة) باستخدام مركبات الإيبيسبول. وفيما يلي معايير الاستبعاد:(1)تقارير الحالات أو سلسلة القضايا (2) دراسة واحدة (3) دراسة تسجيل المرضى الأطفال أو المواليد الجدد (4) عقد مؤتمرات أو ملصقات (5) دراسة حيوية للصيادلة (6) في دراسة فيترو ولتفادي التحيز، كان اثنان من المؤلفين (تشانغ لان) مسؤولين عن تفتيش المواد وفحصها. وإذا لم يوافق صاحب البلاغ الثاني على ذلك، فإن كاتباً آخر (ليلي) سيساعد على حل المسألة ويتخذ القرار النهائي. وشملت البيانات التي جُمعت المؤلفين، وسنة النشر، والدراسة، والمدة، والخصائص الديمغرافية للمرضى، والاستجابة السريرية، وخطر المؤسسات التعليمية. The Cochrane Risk for Bias Assessment tool was used to assess the risk of bias for RCTs in this meta-analysis (23)وقد أُعفيت هذه الدراسة من الموافقة على الأخلاقيات في المركز الطبي في تشي ماي، حيث قام مؤلفو الدراسة بجمع وتوليف البيانات من التجارب السريرية السابقة التي حصل فيها محققو المحاكمات بالفعل على موافقة مستنيرة. وقد اتبع هذا الاستعراض المنهجي المبادئ التوجيهية لبنود الإبلاغ المفضلة لإجراء استعراضات منهجية وتحليلات دقيقة، وقد سُجِّل في البرنامج.

التعريف والنتائج وكانت النتيجة الرئيسية هي الاستجابة السريرية لاختبار العلاج. وشملت النتائج الثانوية الاستجابة السريرية المبكرة في نقاط زمنية مبكرة، وخطر الإصابة بمرض الإيدز، ألا وهي العلاجات المسببة للمرض، ودراسة الأمراض التي تنتقل بالاتصال الجنسي المتصلة بالمخدرات، والإعانات البيئية الخطيرة، والتوقف عن العمل بسبب الأمراض المعدية، والوفيات. وعُرِّف تقرير المصير على أنه تخفيض بنسبة 20 في المائة في حجم السقوط بالمقارنة مع خط الأساس، وعُرِّفت الخطة المتوسطة الأجل بأنها 48 إلى 72 ساعة بعد أول ضخ للمخدرات الدراسية. أجري تحليل إحصائي باستخدام مدير استعراض البرامجيات، النسخة 5-3. The degree of heterogeneity was evaluated with the Q statistic generated from the X(2) اختبار. وقُيِّمت نسبة التغاير الإحصائي باستخدام التدبير I2. وقد عُرِّف التجانس بأنه ذو أهمية عندما تكون قيمة الفئتين أقل من 0.1 أو 2 أكثر من 50 في المائة. وقد طُبِّق نموذج للآثار الثابتة ونموذج التأثيرات العشوائية عندما تعتبر البيانات متجانسة أو غير متجانسة، على التوالي. وقد حُسبت نسبة المخاطر المجمّعة ونسبة 95 في المائة من فترات الثقة، واعتبرت قيمة تعادل 0.05 باهظة من الناحية الإحصائية.
النتائج
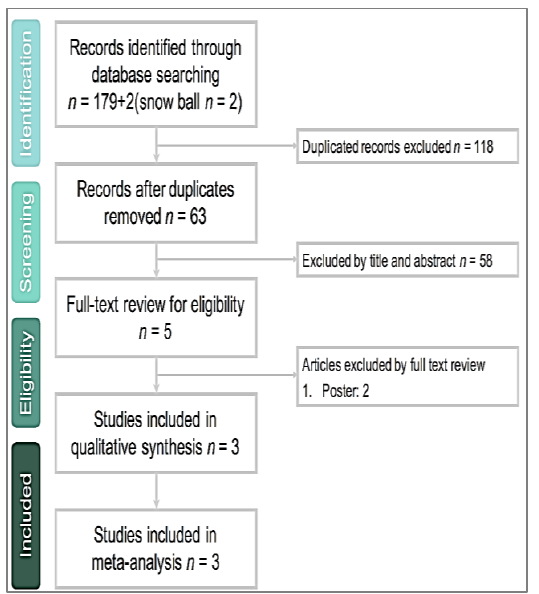
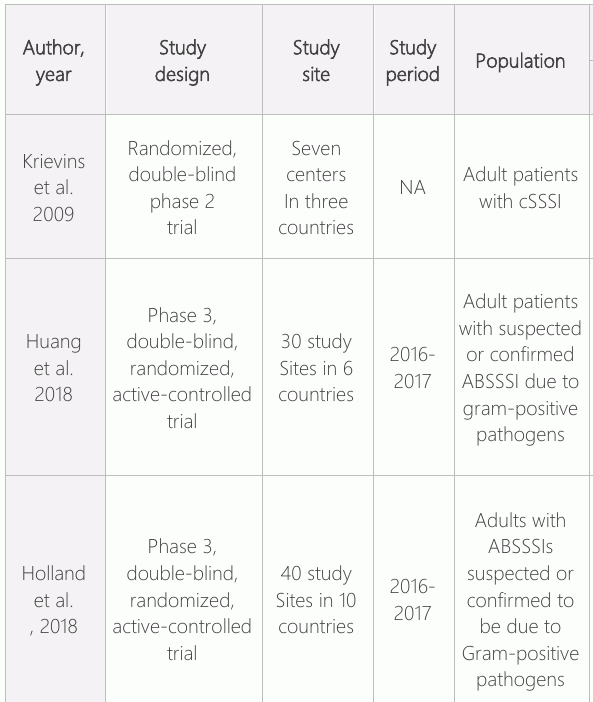
اختيار الدراسة وخصائصها The search program initially yielded 181 references, and then, 63 articles were screened after excluding 118 duplicated articles. وأخيراً، حُددت 5 مواد لإجراء استعراض شامل للأهلية. مجموع 3 دراسات فقط (19–21) وصممت لمقارنة الكفاءة السريرية والسلامة في النسيج والفانكومسين في معالجة هذه الميثان (الشكل 1 والتذييل 1). وعموماً، شمل هذا التحليل ما مجموعه 1260 مريضاً، من بينهم 625 مريضاً في مجموعة إيكلابريم و635 مريضاً في مجموعة الفانكومسين. All included studies were multicenter and multinational RCTs. واحد كان محاكمة المرحلة الثانية (19) وكانت محاكمات المرحلة الثالثة من المرحلة الثانية (20, 21) (الجدول 1). The duration of antibiotic use was 10 days in one study (19) 5-14 يوما في دراستين أخريين (20, 21)- حدد ما مجموعه 324 مريضا و 268 مريضا مسببات للأمراض في مجموعات النسيج والفاكسوكيسين، على التوالي. في محاكمة المرحلة الثانية (19) وقُيِّمت جرعتان - 0.8 ملغم/كغم و1.6 ملغم/كغم من الكبريت. واستخدمنا المجموعة التي أعطيت ١,٦ ملغم/كغم من النيكلبريم - وهي الجرعات العلاجية - في تحليل الكفاءة السريرية واستخدمت كلتا المجموعتين )٠,٨ ملغم/كغم و ١,٦ ملغم/كغم( في تقييم السلامة. ومن بين المرضى المصابين، كان س. أوريوس أكثر الممرضات شيوعاً، حيث بلغ 68.5 في المائة (ن = 222) و71.3 في المائة (ن=191) في المجموعتين الفلسفية والفانكورسينية، على التوالي. Among S. aureus infections, MRSA was implicated in 100(40.1%) and 82(35.6%) infections in the iclaprim and vancomycin groups, respectively. ويظهر الشكل 2 خطر التحيز في كل دراسة، ويرتبط معظمها بتدني خطر التحيز.
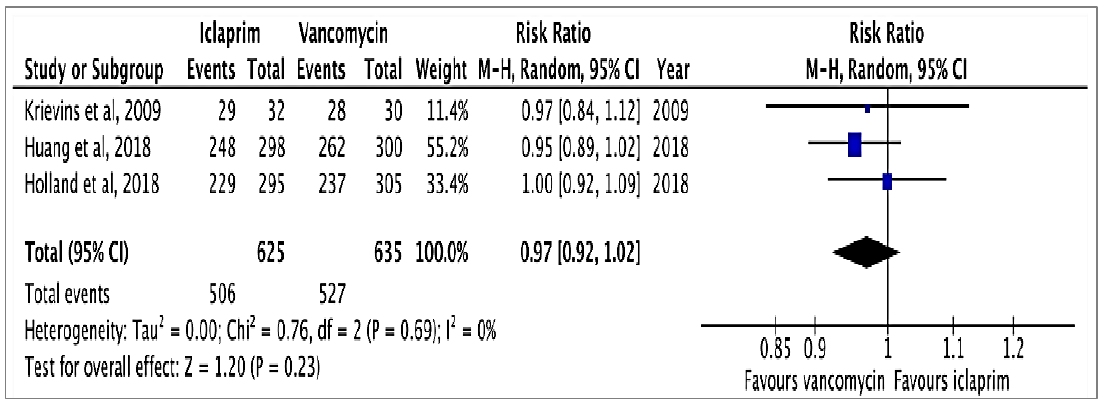
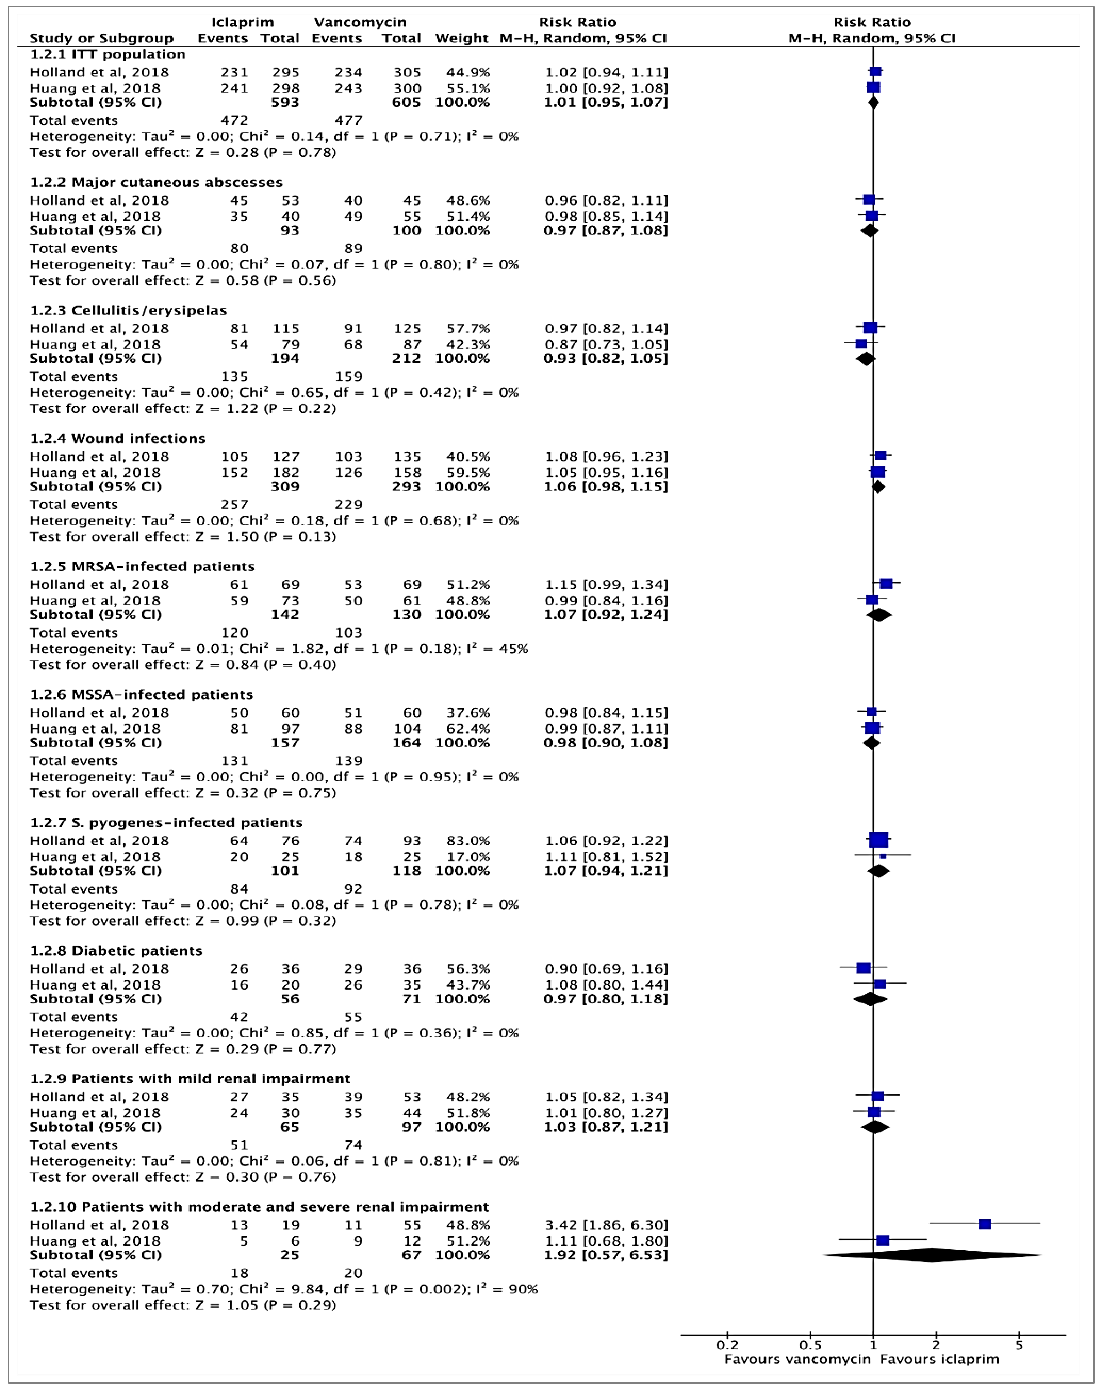
الكفاءة السريرية The pooled analysis of the 3 enrolled trials revealed that the clinical treatment rate at TOC was 81.0% (506/625) and 82.3% (527/635) in the intention-to-treat (ITT) group of patients who received iclaprim and vancomycin, respectively. وعموماً، كانت معدلات العلاج السريري مماثلة في كل من إكلامبريم وفانكومسين (R, 0.97; 95 في المائة من الـ CI, 0.92-1.02, I2=0%, Fig 3). وقد كشف تحليل الحساسية بعد حذف دراسة فردية في كل مرة عن نفس النتائج. محاكمات المرحلة الثالثة فقط (20, 21) Report the findings of ECR at ETP. No differences were observed regarding ECR and ETP in ITT populations between the iclaprim and vancomycin groups (80% vs 78.8%; RR, 1.01; 95% CI, 0.95-1.07, I2=0%, Figure 4). In the subgroup analysis, iclaprim and vancomycin exhibited similar ECRs in the 3 types of ABSSSIs: major cutaneous abscesses (RR, 0.97; 95%CI, 0.87-1.08, I2=0%), cellulitis/erysipelas (RR, 00693; 95%CI, 082-1.05 wound, I20%), كما كان إيكلابريم وفانكومسين فعالين على نحو مماثل ضد 3 أنواع من المسببات: MRSA (R, 1.07; 95%CI, 0.92-1.24, I2=45%), MSSA (RR, 0.98; 95%CI, 090-1.08, I2=0%), and Streptococcus pyogenes infections (RR, 1.07; 95%CI, 0. وأظهرت العقاقير المخدرة مرة أخرى فعالية مماثلة في المرضى المصابين بمرض السكري (R, 0.97؛ 95 في المائة من المصابين بفيروس نقص المناعة البشرية؛ 0.80-1.08؛ I2=0%) وذوي الإعاقة الكلوية (الدرجة المتوسطة: 1.03؛ 95 في المائة من المصابين بمرض السكري؛ 0.87-1.21؛ I2=0 في المائة؛ درجة متوسطة وشديدة: 1.92؛ 95 في المائة في المائة في السنة الدولية؛ 0.57-6.53، I2 في المائة في المائة.90 في المائة.
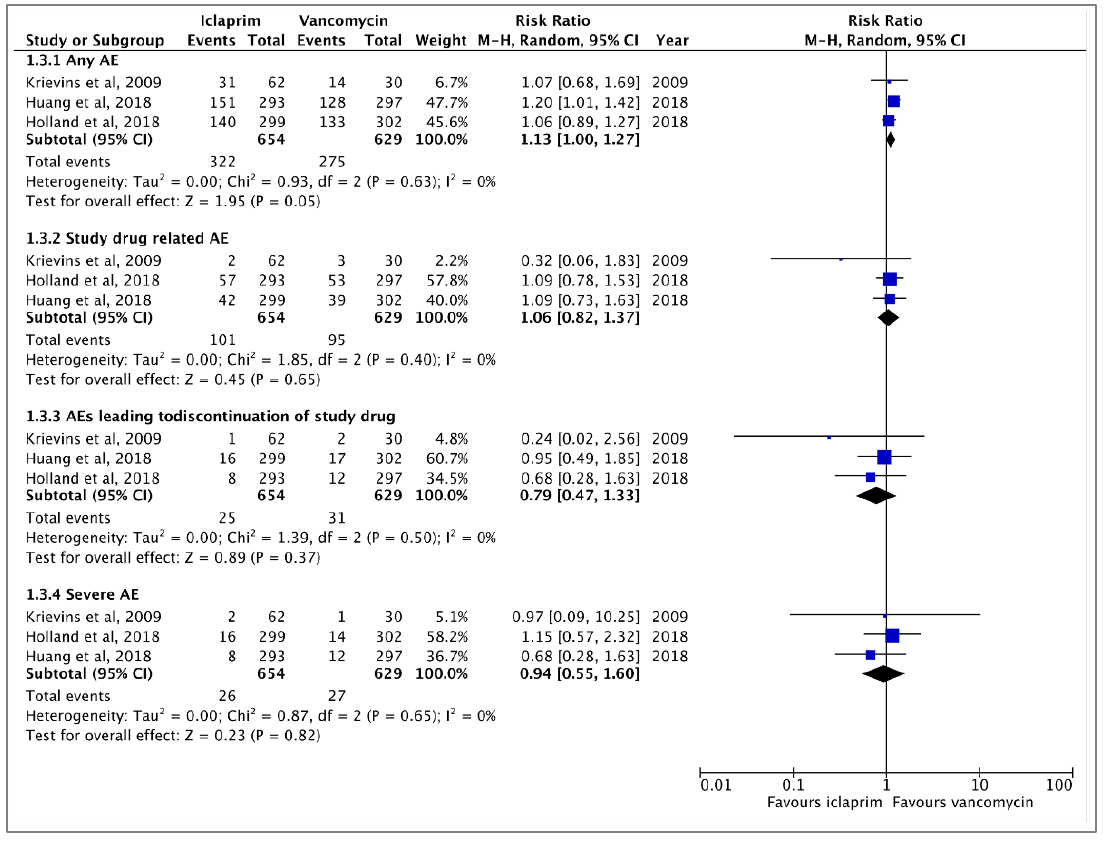
أحداث عكسية In the pooled analysis of the risk of AEs, iclaprim and vancomycin were associated with similar risks in terms of any AE (RR, 1.13; 95% CI, 1-1.27, I2=0%), drug-E (RR, 1.06; 95% CI, 082-0,370%, I2%), discontinuation of study drug due to AE (RR, 0.79; Although iclaprim was associated with a lower risk of nephrotoxicity than vancomycin, the difference did not reach a difference (0% vs. 0.3%; RR, 0.17; 95%CI, 0.17-1.40, I2=0) in the pooled analysis of two RCTs (20, 21)وأخيراً، أُبلغ عن وفيات جميع الأسباب في طائرتين من طراز RCT؛ ولم يُبلَّغ عن حدوث وفيات في مرضى أصيبوا بسكتة قلبية، ولكن حدثت ثلاث وفيات (0.5 في المائة) في مرضى تلقوا فانكومسين.
المناقشة
This meta-analysis enrolled a total of three RCTs19-21 involving 1260 patients with ABSSSIs, including 625 and 635 patients receiving iclaprim and vancomycin, respectively. وإجمالاً، أشارت النتائج التي توصلنا إليها إلى أن " إيلامبريم " غير أدنى من شركة فانكومسين في معالجة " ABSSSIs " ، وأن هذه النتائج مدعومة بالأدلة التالية. فأولاً، كان معدل العلاج السريري في منطقة إيكلامبريم 81 في المائة من سكان المنظمة، وهو ما يماثل معدل الفانكومسين (82.3 في المائة). ولا يزال هذا التخلف عن خصخصة فانكومسين هو نفسه في تحليل الحساسية. The non-inferiority of iclaprim to vancomycin in terms of early responses remained consistent across various populations, including different types of ABSSSIs (major cutaneous abscesses, cellulitis/erysipelas, and wound infection), different pathogens (MRSA, MSSA and S. pyogenes), and different underlying comorbidity (diabetes and re woundnalment). وتتفق هذه النتائج مع نتائج الدراسات السابقة - تحليل مجمّع للمرحلتين 3 من أفرقة الاستعراض الإقليمي (24, 25)ونتائج دراسة هوانغ وآخرون (2, 6) وكان معدل الاستجابة السريرية في مرحلة مبكرة أعلى (85.8 في المائة؛ 95 في المائة في كل عام، 81.5 في المائة - 89.4 في المائة) بالمقارنة مع شركة فانكومسين (79.8 في المائة؛ 95 في المائة في المائة في عام 1999؛ 74.8 في المائة في عام 84.2 في المائة) في صفوف المرضى المصابين بمرض فيروس نقص المناعة البشرية الذين يتعاطون المخدرات عن طريق الحقن. غير أن النتائج التي توصلنا إليها استندت إلى 3 فحوصات طبية ذات عدد أكبر من المرضى وإلى تحليل أكثر بكثير من المجموعات الفرعية. وتظل جميع النتائج متسقة في التحليل العام وكذلك في كل تحليل من تحليلات الأفرقة الفرعية، حتى يمكن لنتائجنا أن تؤكد كذلك الفعالية الإكلينيكية. In summary, the clinical efficacy of iclaprim in the treatment of ABSSSIs was non-inferior to that of vancomycin based on this meta-analysis.
ثانياً، ينبغي للمستوصفين أن ينظروا في قضايا السلامة عند فرض مضادات حيوية جديدة لمعالجة الإصابات البكتيرية الحادة. In the pooled analysis of the risk of AEs, iclaprim and vancomycin had similar risks in terms of any AE, serious events, discontinuation of study drug due to AE, and mortality. Moreover, none of the patients receiving iclaprim had drug-related nephron-toxicity, but 0.3% (5/599) of patients receiving vancomycin had nephrotoxicity in the two Phase-III trials (20, 21)وعموما، تشير النتائج التي توصلنا إليها إلى أن سلامة النشوة مماثلة أيضا لسلامة الفانكومسين.
وينطوي هذا التحليل على عدة قيود ينبغي معالجتها. First, only 3 RCTs were enrolled; thus, the number of included patients was limited. Second, only one RCT19 reported the microbiological outcome, in which microbiological eradication rates for gram-positive pathogens at the TOC visit were 26/29 patients (90%) for iclaprim at 0.8 mg/kg, 24/30 (80%) for iclaprim at 1.6 mg/kg, and 18/25 (72%) for vancomycin. وكان معدل الاستئصال الميكروبيولوجي لس. أوريوس في ثلاث مجموعات علاجية هو 12/15 مريضا (8 في المائة)، و 13/18 مريضا (72 في المائة)، و 10/17 مريضا (59 في المائة)، على التوالي. وحتى ٥ مرضى من قبيلة MRSA - بما في ذلك ٤ مرضى من ٠,٨ ملغم/كغ-كلامبريم وواحد من مجموعة فانكومسين - كانوا جميعاً معالجين طبياً بالميكروبيولوجيا. غير أنه يلزم إجراء دراسات إضافية واسعة النطاق للتحقيق في هذه المسائل.
خاتمة
ويوحي هذا التحليل المميت بأن النيكلبري يُظهر كفاءة غير أدنى مقارنة بالفانكومسين في معالجة هذه المؤسسات. In addition, iclaprim is generally well tolerated as vancomycin, with an even lower incidence of nephrotoxicity.
الإقرارات
- مساهمات المؤلفين (CRediT)
- ساهم جميع المؤلفين بالتساوي في جميع أدوار CRediT الأربعة عشر (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- التمويل
-
Funding information was not reported in the published version of this article.
- تضارب المصالح
- All authors declare there is no conflict of interest
- الموافقة الأخلاقية
- Ulutas Med J 2022;8(3):100-109 Figure 2. The risk of bias in each domain This study was exempt from ethics approval of Chi Mei Medical center as the study authors just collected and synthesized data from previous clinical trials in which informed consent has already been obtained by the trial investigators.
- إتاحة البيانات
- A data availability statement was not reported in the published version of this article.
المراجع (26)
25 من أصل 26 مرجعًا مرتبطة بمعرّف DOI.
- Soriano A, Stefani S, Pletz MW, Menichetti F. Antimicrobial stewardship in patients with acute bacterial skin and skin structures infections: an international Delphi consensus. J Glob Antimicrob Resist. 2020;22:296-301. DOI Crossref PubMed Google Scholar
- Moran GJ, Abrahamian FM, Lovecchio F, Talan DA. Acute bacterial skin infections: developments since the 2005 Infectious Diseases Society of America (IDSA) guidelines. J Emerg Med. 2013;44(6):e397-412. DOI Crossref PubMed Google Scholar
- Garau J, Ostermann H, Medina J, Avila M, McBride K, Blasi F. Current management of patients hospitalized with complicated skin and soft tissue infections across Europe (2010-2011): assessment of clinical practice patterns and real-life effectiveness of antibiotics from the REACH study. Clin Microbiol Infect. 2013;19(9):E377-85. DOI Crossref PubMed Google Scholar
- Falcone M, Concia E, Giusti M, Mazzone A, Santini C, Stefani S, et al. Acute bacterial skin and skin structure infections in internal medicine wards: old and new drugs. Intern Emerg Med. 2016;11(5):637-48. DOI Crossref PubMed Google Scholar
- Roshdy D, Jaffa R, Pillinger KE, Guffey J, Rozario N, Davidson L, et al. Effect of a multifaceted stewardship intervention on antibiotic prescribing and outcomes for acute bacterial skin and skin structure infections. Ther Adv Infect Dis. 2018;5(6):103-9. DOI Crossref PubMed Google Scholar
- Jenkins TC, Sabel AL, Sarcone EE, Price CS, Mehler PS, Burman WJ. Skin and soft-tissue infections requiring hospitalization at an academic medical center: opportunities for antimicrobial stewardship. Clin Infect Dis. 2010;51(8):895-903. DOI Crossref PubMed Google Scholar
- Bassetti M, Carnelutti A, Righi E. The role of methicillin-resistant Staphylococcus aureus in skin and soft tissue infections. Curr Opin Infect Dis. 2017;30(2):150-7. DOI Crossref PubMed Google Scholar
- Bassetti M, Baguneid M, Bouza E, Dryden M, Nathwani D, Wilcox M. European perspective and update on the management of complicated skin and soft tissue infections due to methicillin-resistant Staphylococcus aureus after more than 10 years of experience with linezolid. Clin Microbiol Infect. 2014;20 Suppl 4:3-18. DOI Crossref PubMed Google Scholar
- Stevens DL, Bisno AL, Chambers HF, Dellinger EP, Goldstein EJ, Gorbach SL, et al. Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America. Clin Infect Dis. 2014;59(2):e10-52. DOI Crossref PubMed Google Scholar
- Tirupathi R, Areti S, Salim SA, Palabindala V, Jonnalagadda N. Acute bacterial skin and soft tissue infections: new drugs in ID armamentarium. J Community Hosp Intern Med Perspect. 2019;9(4):310-3. DOI Crossref PubMed Google Scholar
- Lan SH, Lin WT, Chang SP, Lu LC, Chao CM, Lai CC, et al. Tedizolid Versus Linezolid for the Treatment of Acute Bacterial Skin and Skin Structure Infection: A Systematic Review and Meta-Analysis. Antibiotics (Basel). 2019;8(3). DOI Crossref PubMed Google Scholar
- Lan SH, Chang SP, Lai CC, Lu LC, Chao CM. The efficacy and safety of omadacycline in treatment of acute bacterial infection: A systemic review and meta-analysis of randomized controlled trials. Medicine (Baltimore). 2019;98(51):e18426. DOI Crossref PubMed Google Scholar
- Lan SH, Lai CC, Lu LC, Chang SP, Huang HT. Efficacy and safety of delafloxacin in the treatment of acute bacterial skin and skin structure infections: a systematic review and meta-analysis of randomized controlled trials. Infect Drug Resist. 2019;12:1415-23. DOI Crossref PubMed Google Scholar
- Lan SH, Chang SP, Lai CC, Lu LC, Chao CM. Ceftaroline Efficacy and Safety in Treatment of Complicated Skin and Soft Tissue Infection: A Systemic Review and Meta-Analysis of Randomized Controlled Trials. J Clin Med. 2019;8(6). DOI Crossref PubMed Google Scholar
- Hawser S, Lociuro S, Islam K. Dihydrofolate reductase inhibitors as antibacterial agents. Biochem Pharmacol. 2006;71(7):941-8. DOI Crossref PubMed Google Scholar
- Peppard WJ, Schuenke CD. Iclaprim, a diaminopyrimidine dihydrofolate reductase inhibitor for the potential treatment of antibiotic-resistant staphylococcal infections. Curr Opin Investig Drugs. 2008;9(2):210-25. PubMed Google Scholar
- Sader HS, Fritsche TR, Jones RN. Potency and bactericidal activity of iclaprim against recent clinical gram-positive isolates. Antimicrob Agents Chemother. 2009;53(5):2171-5. DOI Crossref PubMed Google Scholar
- Schneider P, Hawser S, Islam K. Iclaprim, a novel diaminopyrimidine with potent activity on trimethoprim sensitive and resistant bacteria. Bioorg Med Chem Lett. 2003;13(23):4217-21. DOI Crossref PubMed Google Scholar
- Krievins D, Brandt R, Hawser S, Hadvary P, Islam K. Multicenter, randomized study of the efficacy and safety of intravenous iclaprim in complicated skin and skin structure infections. Antimicrob Agents Chemother. 2009;53(7):2834-40. DOI Crossref PubMed Google Scholar
- Holland TL, O'Riordan W, McManus A, Shin E, Borghei A, File TM, Jr., et al. A phase 3, randomized, double-blind, multicenter study To evaluate the safety and efficacy of intravenous iclaprim versus vancomycin for treatment of acute bacterial skin and skin structure infections suspected or confirmed to be due to Gram-positive pathogens (REVIVE-2 Study). Antimicrob Agents Chemother. 2018;62(5):e02580-17. DOI Crossref PubMed Google Scholar
- Huang DB, O'Riordan W, Overcash JS, Heller B, Amin F, File TM, et al. A Phase 3, randomized, double-blind, multicenter study to evaluate the safety and efficacy of intravenous iclaprim vs vancomycin for the treatment of acute bacterial skin and skin structure infections suspected or confirmed to be due to Gram-positive pathogens: REVIVE-1. Clin Infect Dis. 2018;66(8):1222-9. DOI Crossref PubMed Google Scholar
- Huang DB, File TM, Jr., Torres A, Shorr AF, Wilcox MH, Hadvary P, et al. A phase II randomized, double-blind, multicenter study to evaluate efficacy and safety of intravenous iclaprim versus vancomycin for the treatment of Iclaprim Versus Vancomycin Shao-Huan Lan et al. nosocomial pneumonia suspected or confirmed to be due to Gram-positive pathogens. Clin Ther. 2017;39(8):1706-18. DOI Crossref PubMed Google Scholar
- Higgins JP, Altman DG, Gotzsche PC, Juni P, Moher D, Oxman AD, et al. The Cochrane Collaboration's tool for assessing risk of bias in randomised trials. Bmj. 2011;343:d5928. DOI Crossref PubMed Google Scholar
- Huang DB, Corey GR, Holland TL, Lodise T, O'Riordan W, Wilcox MH, et al. Pooled analysis of the phase 3 REVIVE trials: randomised, double-blind studies to evaluate the safety and efficacy of iclaprim versus vancomycin for treatment of acute bacterial skin and skin-structure infections. Int J Antimicrob Agents. 2018;52(2):233-40. DOI Crossref PubMed Google Scholar
- Noviello S, Corey GR, Holland TL, Lodise T, O'Riordan W, Wilcox MH, et al. A pooled analysis of patients with wound infections in the Phase 3 REVIVE trials: randomized, double-blind studies to evaluate the safety and efficacy of iclaprim versus vancomycin for treatment of acute bacterial skin and skin structure infections. J Med Microbiol. 2020;69(4):625-630. DOI Crossref PubMed Google Scholar
- Huang DB, Noviello S, Balser B, Scaramucci A, Corey GR. A pooled analysis of the safety and efficacy of iclaprim versus vancomycin for the treatment of acute bacterial skin and skin structure infections in patients with intravenous drug use: Phase 3 REVIVE Studies. Clin Ther. 2019;41(6):1090-6. DOI Crossref PubMed Google Scholar
اقرأ النص الكامل
افتح ملف PDF هنا
جارٍ تحميل ملف PDF…
إذا لم يظهر ملف PDF هنا، استخدم زر التنزيل أعلاه.
كيف تقتبس هذه المقالة
Lan SH, Chao CM, Chang SP, Lu LC, Hsu TL. Iclaprim Versus Vancomycin for the Treatment of Acute Bacterial Skin and Skin Structure Infection: A Systematic Review and Meta-analysis of Randomized Controlled Trials. Ulutas Med J. 2022;8(3):100-109. doi:10.5455/umj.20220613080211
Lan, S. H., Chao, C. M., Chang, S. P., Lu, L. C., & Hsu, T. L. (2022). Iclaprim Versus Vancomycin for the Treatment of Acute Bacterial Skin and Skin Structure Infection: A Systematic Review and Meta-analysis of Randomized Controlled Trials. The Ulutas Medical Journal, 8(3), 100–109. https://doi.org/10.5455/umj.20220613080211
Lan, S.H. et al. (2022) 'Iclaprim Versus Vancomycin for the Treatment of Acute Bacterial Skin and Skin Structure Infection: A Systematic Review and Meta-analysis of Randomized Controlled Trials', The Ulutas Medical Journal, 8(3), pp. 100–109. doi: 10.5455/umj.20220613080211.