The Ulutas Medical Journal · ISSN 2149-0430 (مطبوع), 2149-388X (إلكتروني) · https://www.ulutasmedicaljournal.com/?mno=160874
مقالة أصلية · وصول مفتوح
تقييم عمليات المتابعة البريدية للأطفال المكلفين بإجراءات غلين
ترجمة آلية للعنوان والملخص والنص الكامل. الأصل الإنجليزي
- Mardin Artuklu Üniversitesi Nur Mh Diyarbakır Yolu Yenişehir Yerleşkesi, 47200 Artuklu/Mardin ROR
- S.B.U. Gazi Yaşargil Training and Research Hospital ROR
الملخص
مقدمة: وتهدف هذه الدراسة إلى تقييم نتائج العلاج، والمضاعفات، والعوامل التي تؤثر على الوفيات في الحالات التي تمت متابعتها بعد التشغيل في وحدة الرعاية المكثفة للأطفال بعد إجراء غلين. المواد والأساليب: The duration of the patients on the pump during wound, transition times to feeding, blood gas and other laboratory parameters, complications developed during follow-up in the intensive care unit, and outus rates were evaluated retrospectively. النتائج: أُنجزت الدراسة لأسباب تتعلق بمرض الالتهاب الثلاثي، وهو التشخيص الأكثر شيوعا (30.2 في المائة). In the evaluation of the relationship between postoperative patient findings and outus, a positive correlation was found between the duration of inotropic support, early extubation, and the duration of HFNC treatment in all patients (p0.05); and a negative correlation was found in terms of the liquid the patients received on the first day after wound (p0.05). In patients who developed complications, a negative correlation was observed only in terms of the liquid they received on the first day after wound (p0.05) Conclusions: In terms of all patients, it was observed that mortality increased with early extubation and prolonged duration of inotropic support and HFNC treatment, and it decreased as the liquid the patients received on the first day after wound decreased. In patients who developed complications, it was only observed that mortality decreased as the liquid the patients received on the first day after wound decreased.
الكلمات المفتاحية
النص الكامل
ترجمة آلية للنص الكامل؛ النسخة المعتمدة هي الأصل الإنجليزي. الأصل الإنجليزي
مقدمة
أمراض القلب الخلقية هي واحدة من أكثر الاضطرابات الخلقية اكتشافاً، وقد تُشاهد في 4 10/1000 ولادة حية، وقد تتطلب تدخلاً جراحياً وقد تكون لها نتائج مميتة (1)- الورم الوظيفي الوحيد، الذي هو نادر بين أمراض القلب الخلقية وله طابع معقد، يشكل ٧,٧ في المائة من أمراض القلب الخلقية التي تشخيصت في مرحلة الطفولة (2).
In complex congenital heart diseases, in which two-ventricle repairs cannot be performed, the bidirectional cavopulmonary anastomosis (BDG = Glenn shunt) procedure is preferred to increase pulmonary blood flow. عملية جراحية واحدة من نوع العمل تنطوي على خطر الاعتلال والوفاة؛ ومن ثم يمكن أن يكون إجراء التقطيع من قبل BDG إنقاذ حياة هؤلاء المرضى (3, 4)The bidirectional Glenn procedure is performed in patients typically before they reach 6 months of age (5).
The first Glenn shunt was anastomosis between the side of the ligated SVC and the distal end of the transacted pulmonary artery and only flowed to the ipsilateral lung; the contralateral lung was being supplied by antegrade flow from the main pulmonary artery. اليوم، يُنفَّذ بي دي جي بشكل حصري تقريباً بوضع طرف واحد من الكافا الأعلى فينا إلى الجانب الأعلى من وصلة الشريان الرئوي البينسي؛ ومن ثم فإن عودة الكهوف العليا تنزف إلى كلتا الرئتين، مما يعني أنها ثنائية الاتجاه (6).
In BDG shunt procedure, it is aimed to increase pulmonary blood flow. This procedure does not change the amount of blood returning to the heart and therefore the heart is not exposed to volume overload. BDG is performed as an medium surgical treatment in which the right ventricle is completely excluded in patients with single ventricle morphology (6, 7).
وتهدف هذه الدراسة إلى تقييم نتائج العلاج، والمضاعفات، والعوامل التي تؤثر على وفيات المرضى الذين تم متابعتهم في مرحلة ما بعد التشغيل في وحدة الرعاية المكثفة للأطفال بعد إجراء غلين شونت.
المواد والأساليب
تصميم الدراسة
In the study, 53 patients who underwent BDG procedure in the PICU between 01/01/2019 and 31/03/2022 and were followed up postoperatively were included. The duration of the patients on pump during wound, duration of anaesthesia, whether they were receiving nitric oxide (NO), sildenafil or sedation, their vasoactive-inotropic scores (VIS), length of stay onميكانيكيal ventilation (MV), extubation times, whether they were receiving high flow nasal cannula (HFNC) oxygen and transition time
التقنية الجراحية
بعد العقم الوسيط في جميع المرضى، تم استئصال الغدة الدرقية تماما. All operations were performed under normo-thermic cardiopulmonary bypass. In patients who did not undergo atrial septectomy, cardiopulmonary by cannulation of the right atrium. In other patients, cardiac arrest was achieved by antegrade blood cardioplegia following aortic-bicaval cannulation, and then atrial septectomy was performed. شريان البطاطس المملّق فوراً في بداية التفاف القلبي وبعد الإصطدام، تم تحويل مقهى فينا الأعلى من المدخل الأيمن للغرفة، وقد تم خنق الجانب الأرضي بنفسه. The superior vena cava end-to-side anastomosis was performed with 7/0 polypropylene sutures to the arteriotomy performed on the anterior aspect of the right pulmonary artery. In some patients, pulmonary artery reconstruction was performed with an autologous pericardial patch treated with glutaraldehyde. عروق الأزيغوس أغلقت بمقطع ولتقليل الضغط على الشريان الرئوي، تم ربط الشريان الرئوي الرئيسي أو وضعت فرقة على الشريان الرئوي. The VIS score was calculated as: dopamine (mig/kg/min) + dobutamine (mig/kg/min) + 10 × milrinone (mig/kg/min) + 100 press x epinephrine (mug/kg/min) + 100 norepinephrine (mig/kg/min) + 000 10 vasoin (U/gmin). The inotrope score was calculated as: dopamine (mig/kg/min) + dobutamine (mig/kg/min) + 100 x epinephrine (mig/kg/min) (8).
التحليل الإحصائي
وأُجري تحليل إحصائي لهذه الدراسة باستخدام النسخة 26 من البرنامج الحاسوبي لنظام SPSS (IBM Corp., Armonk, NY, USA). وتشمل الإحصاءات الوصفية العدد (ن) والنسبة المئوية (نسبة مئوية). وتم تلخيص المتغيرات المستمرة باعتبارها انحرافاً متوسطاً وتقليدياً. واستُخدم معامل الرنك (Searman Rank Correlation) لتقييم البيانات التي تم الحصول عليها. وقُبل مستوى الأهمية الإحصائية على أنه " النقطة المرجعية " ، في جميع الاختبارات.
البيان الأخلاقي
وتم الحصول على الموافقة على الدراسة من لجنة أخلاقيات الممارسات السريرية الجيدة التابعة لمستشفى ديارباكر غازي ياسرجيل للتدريب والبحث (تاريخ الموافقة/الوكالة الدولية: 20.05.2022/96).
النتائج
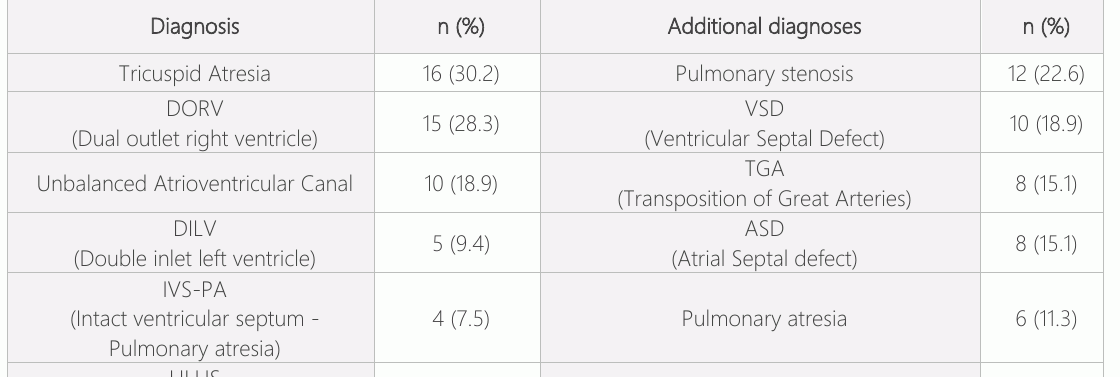
In the study, 32 of the 53 patients, who were followed up in the Pediatric Intensive Care Unit after the Glenn shunt procedure, were male and 21 were female. وقد أُنجزت هذه الدراسة بسبب الالتهاب الرئوي، وهو التشخيص الأكثر شيوعاً (30.2 في المائة). وكان التشخيص الاضافي الأكثر شيوعا هو السمنة الرئوية (22.6 في المائة) (الجدول 1).
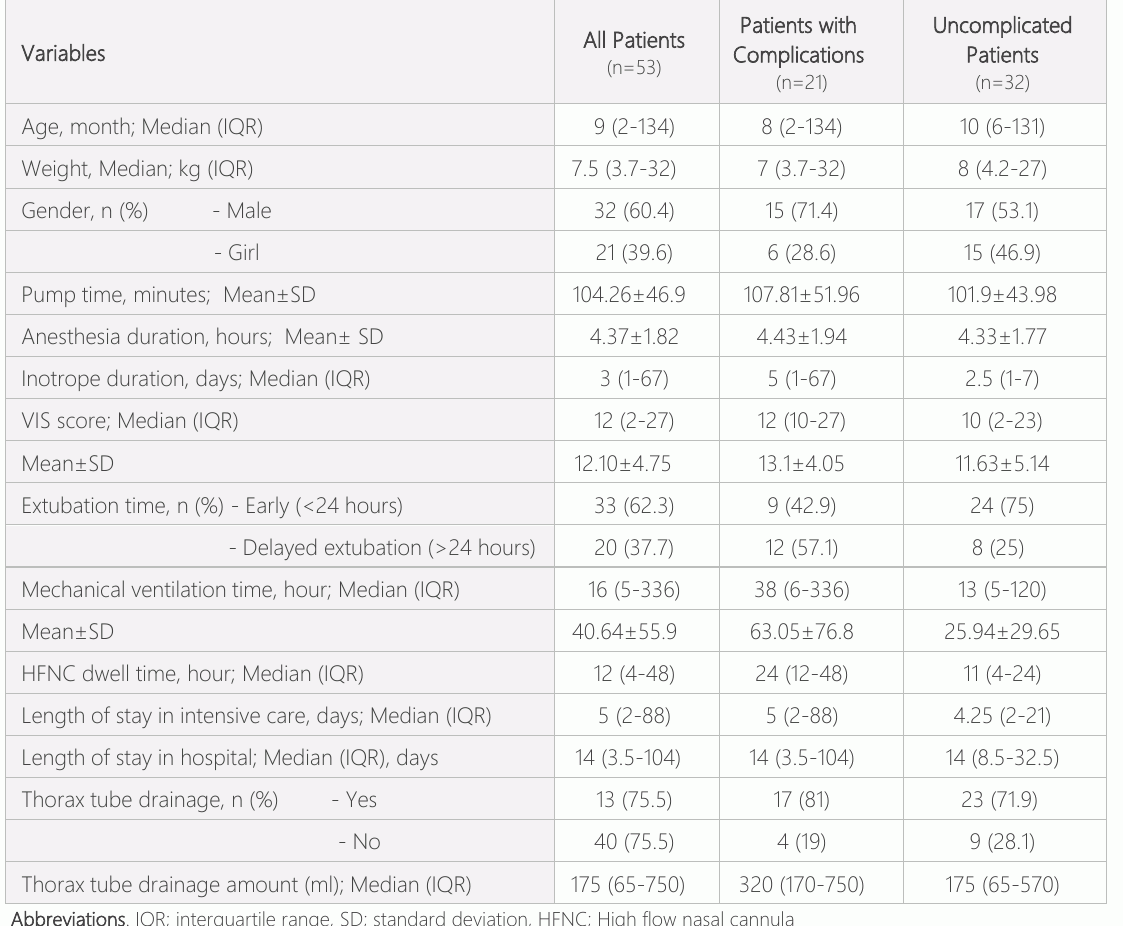
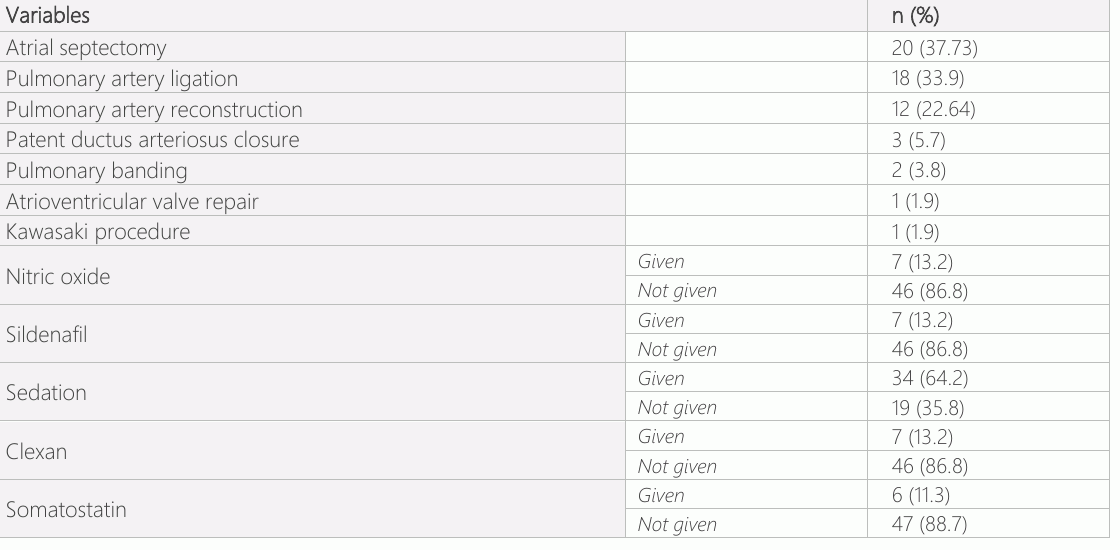
وكان متوسط العمر 15.21 شهر (IQR;2-134). The mean duration of anesthesia was 4.371.82 hours and the mean duration of the patients on pump was 104.2646.90 minutes. وكان متوسط مدة الدعم غير المادي 3 أيام (المعيار IQR؛ 1-67) The mean VIS score of the patients was 12.14.75. وقت تبديل المضادات الحيوية كان 321.40 يوم The median extubation time (length of stay onميكانيكيal ventilation) of the patients was 16(IQR;5-336), the median length of stay in the intensive care unit was 5(IQR;2-88) days, and the median length of hospital stay was 14(IQR;3.5-104) days. وتم طرد ثلاثة وثلاثين من المرضى في غضون 24 ساعة، وطرد 20 مريضا بعد أكثر من 24 ساعة (الجدول 2). In patients who underwent BDG, atrial septectomy was the most frequent additional surgical intervention, which was performed in 20 (37.73%). Other additional procedures were pulmonary artery ligation, pulmonary artery reconstruction, PDA closure, pulmonary artery banding, AVvalverepair and surgical procedure for Kawasaki, respectively (Table 3). وترد في الجدول 3 الإجراءات الإضافية والعلاجات الطبية التي أجريت في المرضى.
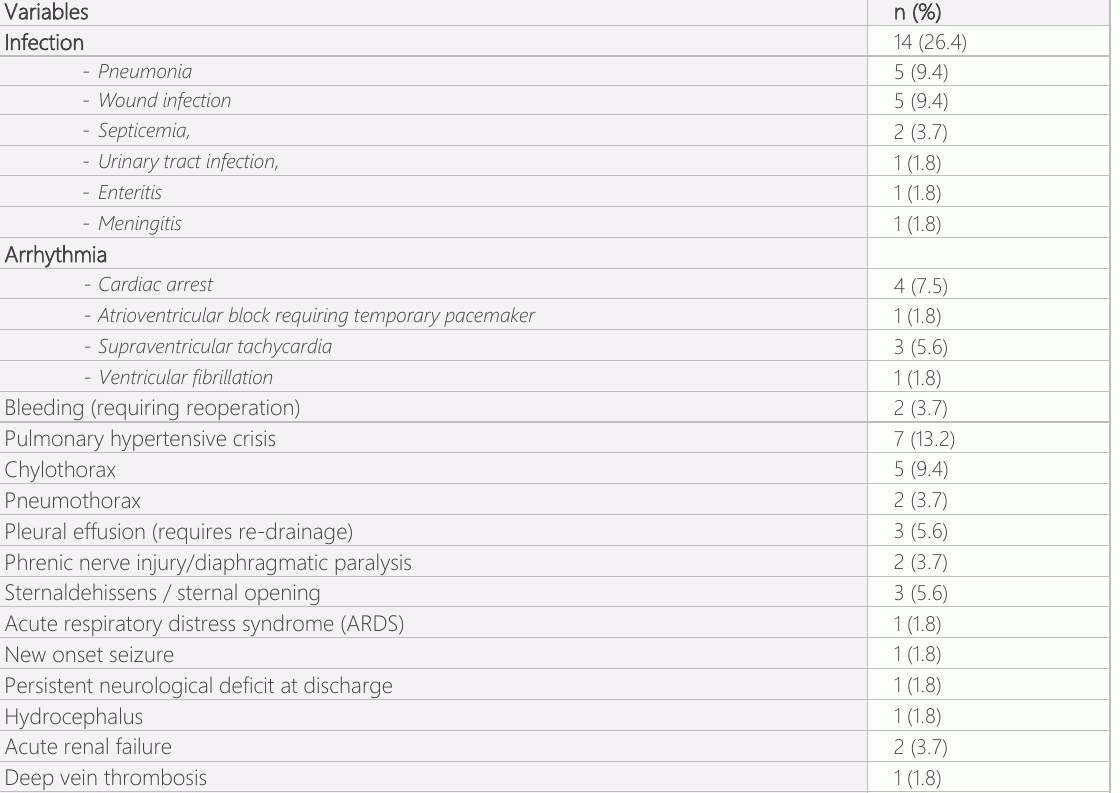
The mean time to the initiation of Clexane treatment was 1.861.07 days. وأُديرت الوقاية من المضادات الحيوية بعد الولادة لجميع المرضى. وقت تبديل المضادات الحيوية كان 321.4 يوم لا توجد مضاعفات تطورت في 32، بينما تطورت بعض التعقيدات في 21 مريضا. وكانت أكثر التعقيدات شيوعا هي العدوى (التي تطورت في 15 مريضا). وكانت أكثر الأمراض شيوعا هي الإصابة بالإصابة، والالتهاب الرئوي، والتهاب السحايا، والتهاب السحايا، على التوالي. تم إعلان خمسة (94.3 في المائة) من المرضى الذين خضعوا غلين خروجاً (الجدول 4). In the evaluation of the relationship between postoperative patient findings and outus, a positive correlation was found between the duration of inotropic support, early extubation, and the duration of HFNC treatment in all patients (p0.05); and a negative correlation was found in terms of the liquid the patients received on the first day after wound (p0.05). In patients who developed complications, a negative correlation was observed only for the liquid they received on the first day after wound (p0.05) (Table 5).
المناقشة
In our study, complications were observed in 21 of the children who underwent Glenn procedure, and 5 patients were declared outus. A negative correlation was found between the findings of the patients who were declared outus and the age, duration on pump, duration of anesthesia, length of stay in the intensive care unit, length of hospital stays, liquid received on the first day after wound, and nitric oxide treatment status of the patients who developed complications. Among these, only correlation in terms of the liquid they received on the first day after wound was significant.
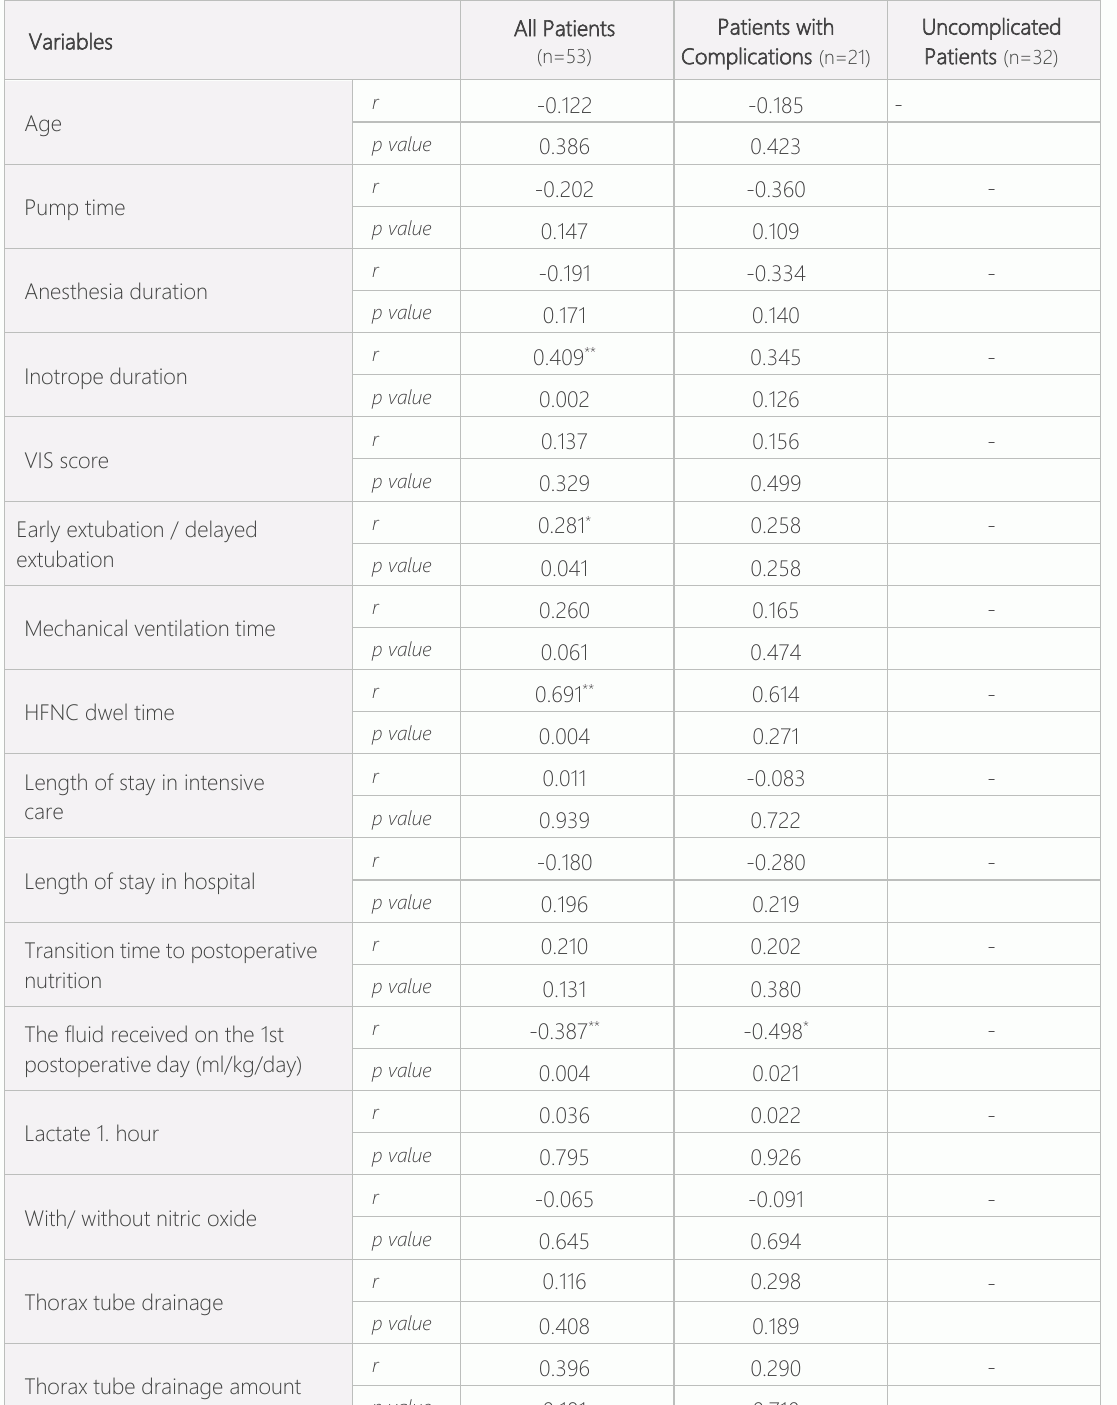
وكان هناك ارتباط إيجابي بين المضاعفات الأخرى، وهو أمر غير هام. In the study conducted by Meyer et al., the duration of anesthesia andurg were longer in the group with post-operative complications, and the administration of perioperative nitric oxide was found to be an important risk factor for complications in the patients (9)- وفي الدراسة التي أجراها تان وآخرون، أُبلغ عن حدوث مضاعفات بنسبة 13.7 في المائة. (10).
In the study of Shidhika et al., postoperative infectious complications were observed in 27.6% of 193 patients operated for congenital heart diseases (including 11 BDG) and acquired heart diseases. In the same study, 26.3% of the patients with infection were diagnosed with postoperative pneumonia (11)ولوحظ في دراسة أجريت في نيجيريا أن 13.7 في المائة من مرضى جراحة القلب أصيبوا بعدوى أقل من الجهاز التنفسي. وفي دراستنا، لوحظت مضاعفات معدية في 26.4 في المائة من المرضى. 35.7 في المائة من المضاعفات المعدية هي الالتهاب الرئوي و 35.7 في المائة من الإصابة بالنسيج الناعمة (12)- وكانت البيانات الواردة في دراستنا متسقة مع الدراسات التي أجريت سابقا.
الجاذبية هي أكثر الأسباب شيوعاً للإصابة بالعدوى الاجتماعية في الأطفال بعد جراحة القلب (13)- في دراسة أجريت على البكتيريا معزولة عن عينات الطموحات الشقية، كانت نسبة 54 في المائة من البكتيريا من البكتيريا من نوع Pseudomonas aeruginosa، و16 في المائة من البكتيريا (Acinetobacter baumannii)، و8 في المائة من البكسكو أوريوس (14)وفي دراستنا، عثر على ستافيلوكوكسكوم في عينات الدم للمرضى، وعثر على ستينوتروفيوناس فيليا، وأسينيتوبكتور إيوفتي، ومصنع، وكانديدا، وأسينتيوبتيكر باوماني، في عينات الطموحات الاصطناعية. وقد لوحظت في ثقافة الجروح، كما لوحظ في ثقافة البول. وكان المعدل المرتفع للبكتيريا الغرامية التي عثر عليها في دراستنا مماثلا لنتائج الدراسات الأخرى.
In the study of Kogon et al., it was found that patients with complications had prolonged ICU and hospital stays (15)التي كانت مماثلة لنتائج دراستنا
In some patients with balanced circulation as a result of bidirectional Glenn shunt procedure, any intervention prior to cavopulmonary anastomosis is not required; however, the majority of them are subjected to preliminary procedures in early infancy. The modified Blalock-Tausig shunt is required for right side structures, the Norwood procedure for left side structures, and pulmonary arting is required for pulmonary hypercirculation; in the presence of a persistent left superior vena cava, creating bilateral bidirectional superior cavopulmonary anastomosis is necessary (15, 16)وقد قامت هذه الدراسة بتدخلات جراحية إضافية من قبيل التهاب الرئوي، وربط الشريان الرئوي، والضمادات الرئوية.
وتظهر البيانات أن مدة التهوية الميكانيكية، والصرف الصحي، والبقاء في وحدة الرعاية المكثفة والمستشفى قد طالت في المرضى الذين تقل أعمارهم عن 4 أشهر (17)ولوحظ في دراسة كوغون وآخرون أن مدة تصريف أنبوب الصدر ووجود مضاعفات فعالة لا ترتبط بالمضاعفات أو الوفيات (15)وبالمثل، لم يعثر في دراستنا على أي علاقة بين مدة تصريف المياه التكاثرية ووجود مضاعفات فعالة، وطول فترة البقاء في الرعاية والمستشفى المكثفين، والوفيات الجراحية.
After BDG, the upper box and brain are at risk of exposure to high venous pressure, which leads to a low transcranial pressure gradient and may cause neurologic damage. وعلى الرغم من أنه لا يؤدي إلى آثار عصبية كبرى، يمكن ملاحظة حدوث تغييرات في العيادات في الدماغ (18)- وفي دراستنا، لوحظت مضبوطات جديدة في أحد المرضى، ولوحظ عجز عصبي في مريض آخر، استمر بعد تفريغه.
خاتمة
The bidirectional Glenn shunt procedure in cardiac patients with function single ventricle morphology provides an increase in oxygen saturation. ويؤدي ارتفاع معدل تشبع الأوكسجين في التداول المنهجي إلى تحسين نوعية حياة المرضى وانخفاض معدل الوفيات. In terms of all patients, it was observed that mortality increased with early extubation and prolonged duration of inotropic support and HFNC treatment, and it decreased as liquid. The patients received on the first day after the operation decreased. وانخفض معدل الوفيات مع انخفاض السوائل التي يتلقاها المرضى في اليوم الأول بعد الجراحة في المرضى الذين طوروا تعقيدات. ونعتقد أنه ينبغي إجراء مزيد من البحوث والدراسات المتعددة المراكز لتحقيق نتائج أكثر فعالية.
الإقرارات
- مساهمات المؤلفين (CRediT)
- ساهم جميع المؤلفين بالتساوي في جميع أدوار CRediT الأربعة عشر (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- التمويل
-
Funding information was not reported in the published version of this article.
- تضارب المصالح
- The authors declare no conflict of interest.
- الموافقة الأخلاقية
- Approval for the study was obtained from the Good Clinical Practice Ethics Committee of Diyarbakir Gazi Yaşargil Training and Research Hospital (Approval date/ID: 20.05.2022/96).
- إتاحة البيانات
- A data availability statement was not reported in the published version of this article.
المراجع (18)
15 من أصل 18 مرجعًا مرتبطة بمعرّف DOI.
- Hallıoğlu O. Karpuz D. Giray D. Demetgül H. Öztaş A. Doğumsal Kalp Hastalıkları Sıklığının Risk Gruplarına Göre Dağılımı: Fetal Ekokardiyografik Tarama. Jinekoloji-Obstetrik ve Neonatoloji Tıp Dergisi. 2018; 15(1): 1-4. PubMed Google Scholar
- Patrick W O'Leary. Prevalence, clinical presentation and natural history of patients with single ventricle. Progress in Pediatric Cardiology 2002;16(1):31-38. DOI Crossref PubMed Google Scholar
- Blalock A, Taussig HB. The surgical treatment of malformations of the heart in which there is pulmonary stenosis or pulmonary atresia. JAMA 1945; 128: 189-202. DOI Crossref PubMed Google Scholar
- Gleenn WW. Circulatory bypass of the right side of the heart. IV. Shunt between superior vena cava and distal right pulmonary artery; report of clinical application. N Engl J Med 1958; 259: 117-20 PubMed Google Scholar
- Reddy, V. Mohan, et al. Outcomes after bidirectional cavopulmonary shunt in infantsless than 6 month sold. Journal of the American College of Cardiology 1997;29(6): 1365-1370. DOI Crossref PubMed Google Scholar
- Sharma, Rajesh. The bidirectional Glenn shunt for univentricular hearts. Indian Journal of Thoracic and Cardiovascular Surgery 2018; 34(4): 453-456. DOI Crossref PubMed Google Scholar
- Şaşmazel A, Fındık O, Yıldırım A, Fedakar A, Baysal A, Çalışkan A, et al. Tek ventrikül morfolojisine sahip hastalarda çift yönlü Glenn şant işleminin kısa ve orta dönem sonuçları. Turkish J Thorac Cardiovasc Surg 2010;18(2):88-93. PubMed Google Scholar
- Belletti, Alessandro. Vasoactive-inotropicscore: evolution, clinical utility, and pitfalls. Journal of cardiothoracic and vascular anesthesia 2021;35(10):3067-3077. DOI Crossref PubMed Google Scholar
- Meyer, Heidi M., et al. "Outcomes After Bidirectional Glenn Shunt in a Tertiary- Care Pediatric Hospital in South Africa." Journal of Cardio thoracic and Vascular Anesthesia 2022; 36(6): 1573-1581. DOI Crossref PubMed Google Scholar
- Tan, Ann- Marie. Fontan completion rate and outcomes after bidirectional cavopulmonary shunt." European journal of cardio-thoracic surgery 2010; 38(1): 59-65. DOI Crossref PubMed Google Scholar
- Shidhika, Fenny F., et al. "The Namibian Children’s Heart Project: a South–South partnership to provide cardiac care." Cardiology in the Young 2019;29(2): 206-213. DOI Crossref PubMed Google Scholar
- Falase, Bode, et al. Open heart surgery in Nigeria; a work in progress. Journal of cardio thoracic surgery 2013;8: 1-9. DOI Crossref PubMed Google Scholar
- Tan, Linhua, et al. Epidemiology of nosocomial pneumonia in infants after cardiac surgery. Chest 2004;125(2): 410-417. DOI Crossref PubMed Google Scholar
- Kogon, Brian E., et al. The bidirectional Glenn operation: a risk factor analysis for morbidity and mortality. The Journal of thoracic and cardiovascular surgery 2008;136(5): 1237-1242. DOI Crossref PubMed Google Scholar
- Reddy, V. Mohan, John R. Liddicoat, and Frank L. Hanley. "Primary bidirectional superior cavopulmonary shunt in infants between 1 and 4 months of age. The Annals of thoracic surgery 1995;59(5): 1120-1126. DOI Crossref PubMed Google Scholar
- Jaquiss, Robert DB, et al. Early cavopulmonary anastomosis in very young infants after the Norwood procedure: impact on oxygenation, resource utilization, and mortality. The Journal of thoracic and cardiovascular surgery 2004;127(4): 982-989. DOI Crossref PubMed Google Scholar
- Jahangiri, Marjan, et al. Should the bidirectional Glenn procedure be performed through a thorac otomy without cardiopulmonary bypass? The Journal of Thoracic and Cardiovascular Surgery 1999;118(2): 367-368. DOI Crossref PubMed Google Scholar
- Rodriguez, Rosendo A., Nihal A. Weerasena, and Garry Cornel. Should the bidirectional Glenn procedure be better performed through the support of cardiopulmonary bypass? The Journal of Thoracic and Cardiovascular Surgery 2000;119(3): 634-635. DOI Crossref PubMed Google Scholar
اقرأ النص الكامل
افتح ملف PDF هنا
جارٍ تحميل ملف PDF…
إذا لم يظهر ملف PDF هنا، استخدم زر التنزيل أعلاه.
كيف تقتبس هذه المقالة
Talay MN, Doyurgan O. Evaluation of Postoperative Follow-ups of Children Having the Glenn Procedure. Ulutas Med J. 2023;9(3):137-144. doi:10.5455/umj.20230712015152
Talay, M. N., & Doyurgan, O. (2023). Evaluation of Postoperative Follow-ups of Children Having the Glenn Procedure. The Ulutas Medical Journal, 9(3), 137–144. https://doi.org/10.5455/umj.20230712015152
Talay, M.N. and Doyurgan, O. (2023) 'Evaluation of Postoperative Follow-ups of Children Having the Glenn Procedure', The Ulutas Medical Journal, 9(3), pp. 137–144. doi: 10.5455/umj.20230712015152.