The Ulutas Medical Journal · ISSN 2149-0430 (مطبوع), 2149-388X (إلكتروني) · https://www.ulutasmedicaljournal.com/?mno=183589
بحث أصلي · وصول مفتوح
Assessment of Acute Myocardial infarction by the use of special biochemical markers
ترجمة آلية للعنوان والملخص والنص الكامل. الأصل الإنجليزي
- Khartoum College for Medical Sciences, Khartoum, Sudan ROR
- Associate Professor, Department of Clinical Biochemistry College of Medicine, P.O. Box. 641 King Khalid University, Abha, Kingdom of Saudi Arabia - 61421. ROR
- Alghad University, Saudi Arabia
- Sudan University of Science and Technology, Khartoum, Sudan ROR
- Department of Biochemistry, Faculty of Medicine, Omdurman Islamic University, Omdurman, Sudan ROR
الملخص
ويحدث الازدحام القلبي الحادة خلال الفترة التي يعيق فيها التداول إلى منطقة من القلب وينجم عن ذلك التآكل.The objective of this study was to estimate the levels of serum Myoglobin and enzymes as cardiac marker for diagnosis of early Myocardial Infarction.This was case control hospital based study involving 130 patients admitted to Elshaab Teaching Hospital and Sudan Heart Center, suffering chest pain, wherein all patients were taken immediately to Coronary Care Unit (CCU).تم تسجيل 30 شخصاً صحياً على ما يبدو تحت السيطرة.وأجريت هذه الدراسة في الفترة بين آذار/مارس وتشرين الأول/أكتوبر 2010.وتراوح العمر بين 39 و60 سنة.وقد جُمعت عينات من الدم من أجل تقدير ميوغلوبين باستخدام جهاز التلقائي الأوتوماتيكي بالكامل وأنزيمات القلب تم قياسها باستخدام جهاز سبكتروفوتومتر.The mean levels of myoglobin concentration in different patients at admission and after 24 hrs of admission to the hospital was 563 ng/ml and 34 ng/ml for patients and control respectively.The level remained higher even after 24 hrs of admission (414 ng/ml).ورفعت الكيناس الكرياتين ارتفاعاً هائلاً خلال 24 ساعة الأولى في جميع المرضى الذين أُدخلوا إلى المستشفى خلال 6 و10 و20 و24 و48 ساعة عقب الهجوم على آلام الصدر.CK-MB gradually elevated in patients admitted 6, 10, 20, 24 and 48 hrs from chest pain attack, reaching a top after 24 hrs of chest pain attack, and then CK-MB levels declined to normal values after 48 hrs.The LDH level demonstrateded increase levels in patients admitted 6, 10, 20, 24 and 48 hrs from chest pain attack, and the levels persisted all through 24 hrs irrespective of the time admission to the hospital following chest pain.AST level was not elevated after 6 hrs or 10 hrs following the chest pain attack, but a dramatic elevation was seen after 24 hrs following hospital admission, however, increased levels of AST was observed in patients admitted to hospital after 24 or 48 hrs following the attack.The levels were within the normal value in patients admitted after 48 hrs of the chest pain attack, and remain so following 24 hrs of admission.This study indicated that Myoglobin and CK-MB are more sensitive cardiac markers compared to total CK, LDH and AST for the diagnosis of Myocardial Infarction.
الكلمات المفتاحية
النص الكامل
ترجمة آلية للنص الكامل؛ النسخة المعتمدة هي الأصل الإنجليزي. الأصل الإنجليزي
مقدمة
القلب هو عضو منيع مسؤول عن نقل الدم عبر سلسلة من السفن إلى جميع أجزاء الجسم (1)- حدوث ازدحام القلب الحادة خلال الفترة التي يعرقل فيها التداول إلى منطقة من مناطق القلب، وترتب على ذلك تآكل القلب (2)وتتميز الرابطة بألم شديد (المسببات الانجليزية)، وكثيرا ما تكون مرتبطة بالبالور، والطموح، والغثيان، وقلة التنفس، والدوار. وإحدى سلائف شركة AMI هي مادة الكيمياء القلبية، التي تؤدي فيها إعاقة الشريان التاجي إلى حرمان شديد من الأوكسجين من البطيخ قبل الزخرفة. (أنجينا) قد تُعلن خلال استئصال القلب (3, 4).
وتشير الدراسات إلى أن نسبة تتراوح بين 40 و50 في المائة من الـ AMI غير المميتة غير معترف بها من جانب المريض ولا تكتشف إلا في الفحص الروتيني اللاحق أو بعد الوفاة. (5)ومن هذا الزر غير المعترف به، فإن النصف صامت حقا، حيث لا يستطيع المريض أن يتذكر أي أعراض على الإطلاق. (6)The other half of patients with so-called silent infarction can recall an event characterized by symptoms compatible with acute infarction when leading questions are posed after the abnormal ECG is read, unrecognized or silent infarction occurs more commonly in patients without angina, and is more common in patient with diabetes and hypertension.
ويتطلب تشخيص شركة AMI، على النحو الذي حددته رسميا منظمة الصحة العالمية، معيارين على الأقل من المعايير التالية: تاريخ الألم في الصدر، والتغيرات التطوّرية في الحكومة الأوروبية، وارتفاع إنزيمات القلب المتسلسلة (1, 5)وفي كثير من الأحيان، يكون طبيب الفحص واثقاً إلى حد ما بعد الحصول على تاريخ مرضى وإتمام فحص بدني واجراء تنفيذي لفحص الجهاز المغناطيسي الذي حدث. عندما يفشل فريق النقد الأوروبي في إثبات وجود شركة AMI، يجب استخدام علامات القلب (6).
وقد اقتُرحت حتى الآن عدة علامات قلبية، بعضها من قبيل الكرياتين كيناسي؛ ومرض النزيف؛ وكاردياك تروبونين - إي وتروبون - تي؛ وموغلبين؛ والكوليسترول؛ وتريغليسيرايدز؛ وقلة الكثافة؛ وسُلب البروتين؛ وسُبل البروتين العالية الكثافة. (7)2 (CK-2) يتطلب ارتفاعاً من 4 إلى 6 ح لزيادة أعلى من الحد المرجعي الأعلى. وتحدث مستويات بيك في حوالي الساعة الرابعة والعشرين. العودة إلى الوضع الطبيعي يستغرق من 48 إلى 72 ساعة. وتشمل العوامل التي يمكن أن تؤثر على النمط الكلاسيكي حجم الزراعة، وتكوين CK-2 في البطاقة، وإصابة عضلة هيكلية ملازمة، وإعادة التدمير (العفوية؛ وتبعاً للثورمبولية، أو بعد التهاب الكبد) (8, 9).
أما بالنسبة للمرضى الذين يعانون من ازدحام القلبي الحادة، فإن مجموع قيم الدي هيدروجيناس المصنوعة قد ارتفع في الساعة 12: 18 بعد ظهور الأعراض، ووصلت ذروتها إلى 48 ساعة إلى 72 ساعة، وعادت إلى ما دون الحد المرجعي الأعلى بعد 6 إلى 10 أيام. LD-1 (The isoenzyme enriched in the heart) rises within 10h to 12h, tops at 72h to 144h, and returns to normal in approximate 10 days after AMI, paralleling total LD. The elevation patterns of LD-1 and total LD contrast with the elevation patterns of total CK and CK-2, which peak at 24h, and return to below the upper reference limit with 72h after the onset of AMI (10–14)بسبب نصف العمر الذي طال أمده، تعتبر العصبة - 1 علامة حساسة سريريا (90%) للزراعة عندما تستخدم أكثر من 24 ساعة بعد وقوعها (2, 17).
وقد أظهرت الدراسات أن ميوغلوبين علامة حساسة جدا (90-10 في المائة) بالنسبة لشركة AMI. ارتفاع التركيزات السطحية من الأوغلوبين فوق الفترة المرجعية في وقت مبكر يصل إلى ذروة الذروة بعد ذروة الذروة في نطاق يتراوح بين 4 و 12 ساعة، مما يشير إلى أن المصل يرمز إلى المسار المبكّر للتكسير العصبي القلبي (10, 15).
Myoglobin is rapidly clear and thus has a considerably reduced clinical sensitivity after 12 h. If myoglobin is to have a role in detecting AMI, it must be within the first 0-4 h, the time period in which CK-2 (CK- MB) is still within its reference interval (16, 22)كما أن الإفراج التراكمي العام عن " ميوغلوبين " يرتبط بحجم غير مشرد. However, despite these findings, the measurement of serum myoglobin has not been extensively utilized in clinical laboratories for the routine analysis in AMI. The main reason has been the poor clinical specificity (60-95%) of the protein, caused by the large quantities of myoglobin found in skeletal gang (3, 11, 14)وقد أكدت الدراسات الأخرى التي قارنت أنماط " ميوغلوبين " بعلامات " CK-3 " و " إطلاق نشاط " CK " أن " ميوغلوبين " يمكن استخدامه في وقت مبكر جدا (في 90 دقيقة من العلاج بالصدمات الحرارية) للكشف غير المتفشي عن الارتداد، مع التحديد الدقيق (80 في المائة) (15).
Finally, it has been shown that a myoglobin to total CK activity ratio of greater than 5.0 is indicative of reperfusion, with a clinical sensitivity of 75% and a clinical specificity of 96% (19)ومن ثم، فقد استنتج أن حالة التكرار قد تتنبأ بصورة مرضية بعينة واحدة تم الحصول عليها إما وقت القبول، أو لتقييم الارتداد التلقائي، أو في وقت مبكر جدا ().90 دقيقةبعد بدء العلاج بالصدمات (12, 18).
وقد أُجريت هذه الدراسة بهدف رئيسي يتمثل في تقدير المصل الميوغلوبين كعلامة قلبية لتشخيص الازدحام القلبي ومقارنة ذلك بارامترات القلب التقليدية للكشف المبكر عن الضرر الأوقياني.
تصميم الدراسة
واشتملت هذه الدراسة على 130 مريضاً تم قبولهم في مستشفى إلشاب للتدريس، وعانى مركز القلب السوداني من آلام في الصدر، حيث أُخذ جميع المرضى فوراً إلى إدارة وحدة الرعاية البدنية عند وصولهم. وشارك في هذه الدراسة أيضاً 30 موضوعاً صحياً على ما يبدو ليكونوا تحت السيطرة (مجموعة المراقبة التي لا يوجد تاريخها الحالي أو الماضي للزراعة القلبية).
وقد جُمعت عينات الدم (4 ملليتر) مباشرة بعد دخول المستشفى من كل مريض، فضلا عن السيطرة على استخدام الحقن القابلة للتصريف من أجل تقدير إنزيمات القلب ومن أجل ميوغلوبين. All blood samples were allowed to clot at room temperature and then centrifuged at 4000 RPM to obtain the serum. The clear serum was taken immediately for analysis or stored at 2 - 8 Cصفر For 24 hrs for further use.
تم استخدام الـ 7000 ميغاغيا التلقائية الكاملة لقياس ميوغلوبين. واستُخدمت المطياف الدليلي لتحليل إنزيمات القلب. تم شراء جميع الأدوات والمفاعلات من شركة سيغما الكيميائية
Estimation of Myoglobin
ويجري احتضان الخادم في وقت واحد مع العناصر التالية: الجسيمات المغنطيسية المجمّعة بجسد أحادي مضاد للحشرات. A second monoclonal anti-Mgb antibody, which differs from the first and which is conjugated with alkaline phosphatase (AP conjugate).
وبعد تشكيل مجموعة من الجسيمات/مغب/ميغابايت، يتم إزالة الغسيل عن طريق الغسيل. أما نشاط الانزيم المتبقي المتجه إلى الجسيمات فهو يتناسب بشكل مباشر مع كمية الزئبق في العينة (25).
Estimation of Lactate dehydrogenase
Lactate dehydrogenase (LD or LDH) catalyze the reduction of pyruvate by NADH to form lactate and NAD+. The catalytic concentration is determined from the rate of decrease of NADH measured at 340 nm. The standard methods used for measuring LDH are kinetic methods (1, 12).
Estimation of Creatine Kinase
Creatine Kinase (CK) catalyzes the phosphorylation of ADP, in the presence of creatine phosphate, to form ATP and creatine. The catalytic concentration is determined from the rate of NADPH formation, measured at 340 nm, by means of the hexokinase (HK) and glucose-6-phosphate dehydrogenase (G6P-DH) coupled reactions (13).
Estimation of Creatine Kinase-MB
A specific antibody inhibits CK-M subunits but it does not affect to the CK-B subunits. CK-B catalytic concentration, which corresponds to half of CK-MB concentration, is determined from the rate of NADPH formation, measured at 340 nm, by means of the hexokinase (HK) and glucose-6- phosphate dehydrogenase (G6P-DH) coupled reaction (3, 13).
Estimate Aspartate aminotransferase
وتقوم شركة Aspartate aminotransferase (AST/GOT) بتحفيز نقل مجموعة الأمينو من أسبارتايت إلى أكسوغلواتتين، مما يشكل أوكسالات وجلوتامات. The catalytic concentration is determined from the rate of decrease of NADH measured at 340 nm, by means of the malatedehydrogenase (MDH) coupled reaction (12, 13).
النتائج
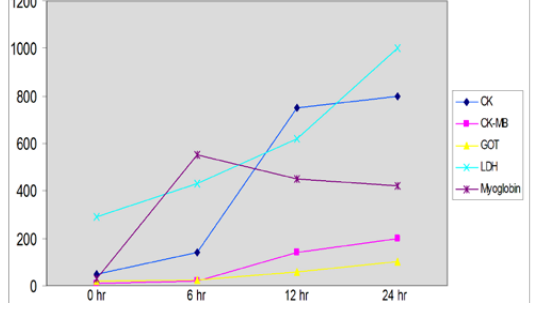
وترد في الجدول رقم 1 مستويات الميولغلوبين، والهيدروجينات، والكيناس الكرياتين، والكيناس المختلط، والأشعة المقطعية، نظراً لأن العلامات الأحيائية للزراعة القلبية خلال 6 و10 و20 و24 و48 ساعة بعد بدء الألم في الصدر، كما تم تحديد نفس المعالم في الشكل رقم 1.
It can be seen that within 6 hrs of onset of chest pain the level of myoglobin was significantly el about 8 fold of normal value and about 16 fold of control value, being 563 ng/ml and 34 ng/ml for patients and control respectively. This level remained higher even after 24 hrs of admission (414 ng/ml).
The same trend was also noted in other groups of patients admitted hospital at 10, 20, 24 hrs following onset of chest pain. The myoglobin level was much reduced in patients admitted to the hospital after 2 days of the inception of chest pain, but was still significantly higher than normal value or control, and continued to be elevated even after 24 hrs of admission. وقد أظهر المرضى الذين أُدخلوا إلى المستشفى بعد 3 أيام من بدء ألم الصدر مستويات منخفضة جداً من الأوغلبين. وانخفض التركيز إلى حوالي القيمة العادية 24 ساعة بعد ذلك.
ورفعت الكيناس الكرياتين ارتفاعاً هائلاً خلال 24 ساعة الأولى في جميع المرضى الذين تم قبولهم في المستشفى خلال 6 و10 و20 و24 و48 ساعة بعد بدء ألم الصدر. The CK began to fall towards normal values after 24 hrs in patients admitted after 48 hrs of chest pain.
CK-MB gradually elevated in patients admitted 6, 10, 20, 24 and 48 hrs from chest pain attack, reaching a top after 24 hrs of chest pain attack, then CK-MB levels declined to normal values after 48 hrs.
The LDH level demonstrateded increase levels in patients admitted 6, 10, 20, 24 and 48 hrs following chest pain attack, and the levels persisted all through 24 hrs irrespective of the time of hospital admission.
AST level was not elevated after 6 hrs or 10 hrs following the chest pain attack, but a dramatic elevation was seen after 24 hrs following hospital admission, however increased levels of AST was observed in patients admitted to hospital after 24 or 48 hrs following the attack. The levels were within the normal value in patients admitted after 48 hrs of the chest pain attack, and remained so following 24 hrs of admission.
It is worth mentioning here that the levels of Myoglobin, CK, CK-MB, LDH and AST were within the normal range in about 28 % of the patients admitted hospital following chest pain attack.
المناقشة
The preliminarily findings obtained from this study revealed that clinical assessment and ECG examinations showed that 72 % of the admitted patients were diagnosed as having myocardial infarction (MI) while 28 % were found to suffer from chest pain.
وقُدِّرت علامات القلب بمجرد قبول المرضى الذين يعانون من أزمة آلام في الصدر في وحدة الاحتجاز المؤقت التابعة لمستشفى الشب ومركز قلب السودان. It appeared that myoglobin concentration was immediately elevated during the first six hours of admission, and remain to be so until 24 hours, this pattern of elevation occurred in all patients with chest pain admitted to CCU at 6 hours, 10 hours, 20 hours and 24 hours of chest pain onset, but patients admitted to CCU after 2 days of the onset of chest pain have shown lower value of myoglobin. In all patients, the level of myoglobin decreased to normal value, these findings are in agreement with the results of Mair, et al (20).
Myoglobin and CK-MB are more sensitive in the first hours of attack and this is in agreement with BIOMACS study that reported on patients with chest pain and a non-diagnostic ECG presenting up to 12 hr from the onset of symptoms. باستخدام عينات دم نصف ساعة للثلاثة أشهر الأولى من الدخول، تبين أن مزيجاً من الميوغلوبين و CK-MB وصل إلى حساسية بنسبة 92 في المائة بعد 2 شهر و 98 في المائة بعد 6 hr مع التحديد بنسبة 93 في المائة (18).
ومن ناحية أخرى، ارتفع كل من الكيناس الكرياتين (CK) وCK-MB تدريجياً في جميع المرضى الذين تم قبولهم في 6 و10 و20 و24 و48 ساعة، ووصل كلاهما إلى ذروتهما بعد 24 ساعة من الهجوم على آلام الصدر. This result is also in line with On the other hand, markers such as LDH and GOT remain changed, e.g. within normal values at the first 6 hours of chest pain attack in patients admitted CCU but serum levels raised sharply after 24 hours reaching an increase of about 263 % and 588 % over the upper reference limit for LDH and GOT respectively. وتتفق هذه النتائج مع نتائج نيوبي وآخرون (21) الذين أبلغوا أنه في نشاط المصل الحاد لـ GOT أدى إلى إثارة عمل رافكيلد وآخرون (22) and Collinson, et al (19) وفي غضون الـ 12 ساعة الأولى، حيث بلغ مستوى الذروة في 24 ساعة من الهضبة المصنوعة، أظهرت مستويات متزايدة في المرضى الذين تم قبولهم في وحدة العناية المركزة في 24 و 48 ساعة من بداية الهجوم على آلام الصدر واستمرت على مستويات عالية حتى بعد 72 ساعة.
وأظهرت عمليات التحويل الجزئية أيضاً ارتفاعاً في القيم ولكن بعد 24 ساعة من الهجوم على آلام الصدر، ولوحظت ذروة في المرضى الذين أدخلوا المستشفى بعد 24 ساعة و48 ساعة من ألم صدرهم، ولكن المرضى الذين أدخلوا إلى المستشفى بعد 24 ساعة من حدوث ألم في الصدر أظهروا قيماً طبيعية للآست. وتتفق هذه النتائج مع النتيجة التي خلص إليها كولينسون وآخرون (19, 23).
وأظهرت عينات الدم التي أخذت في لحظة دخول المرضى إلى المستشفى الذين يعانون من أزمة آلام في الصدر، والذين كان لديهم بداية محددة جيدا من ألم الصدر، أنه خلال فترة الست ساعات الأولى، كانت ميوغلوبين أكثر حساسية من CK، و CK-MB، و LDH، و GOT. During the 10 - 12 hours of chest pain, the sensitivity of CK and CK- MB were higher than other enzymes, then LDH and GOT sensitivity appear in those came after 24 hr of attack (24)وكشفت دراستنا أنه في غضون 6 - 10 ساعات من بداية ألم الصدر، كانت حساسية الـ CK و CK-MB و LDH و GOT (AST) منخفضة للغاية لتبرير قياساتها. كانت حساسية (ميوغلوبين) أكبر بعد النجاح في التبريد المبكر ويصبح ميوغلوبين أكثر حساسية خلال الساعات الست الأولى، في حين أن CK و CK-MB و GOT ليست حساسة بما فيه الكفاية خلال 6-10 ساعات من بداية ألم الصدر. وتتفق هذه النتائج مع نتائج ماير وآخرون (20)وبكر وآخرون (4).
As a decrease of myoglobin concentration was seen after 24 hours of chest pain attack, CK and CK-MB activities raised rapidly in patients admitted to hospital 24 hours after the onset of chest pain. ولوحظت زيادة تبلغ نحو 879 في المائة و 554 في المائة مقارنة بالقيمة القصوى للمراجع بالنسبة للكاكاو وCK-MB على التوالي. هذه النتائج متفقة مع نتائج ويليام (22) and Rarkidle et al (25) وقد أبلغ عن ارتفاع قيمة المصل في المصل بعد ازدهار القلب، بعد حوالي 6 ساعات، ليصل إلى ذروته في 24-30 ساعة ويعود إلى حالته الطبيعية في غضون يومين - 4 أيام.
ساعات أو أكثر والعودة إلى الوضع الطبيعي في غضون 3-5 أيام، في حين أن نشاط الرابطة قد ارتفع في غضون 12-24 ساعة، بلغ ذروته في 48 ساعة (2-4 أيام) ثم يعود تدريجياً إلى حالته الطبيعية من 8 ساعاتth إلى 14 يوم
خاتمة
This study indicated that Myoglobin and CK-MB are more sensitive cardiac markers compared to total CK, LDH and AST for the diagnosis of Myocardial Infarction. ويمكن أن يكون قياس مستوى ميوغلوبين من المساعدة الكبيرة في تأكيد تشخيص الاضطرابات القلبية خاصة في الساعات القليلة الأولى التي تلت بداية ألم الصدر.
وعلامة القلب الأخيرة مثل و(ميوغلوبين) مفيدة جداً في تشخيص الازدحام القلبي الحاد في الساعات الأولى من الهجوم وأكثر حساسية وتحديداً من الانزيم القلبي، وأوصت بإدخال هذا الاختبار في مختبراتنا. Myoglobin, cardiac Tponin I or T should replace CK and CK-MB during the early period following the onset of chest pain.
الإقرارات
- مساهمات المؤلفين (CRediT)
- ساهم جميع المؤلفين بالتساوي في جميع أدوار CRediT الأربعة عشر (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- التمويل
-
Funding information was not reported in the published version of this article.
- تضارب المصالح
- The authors declare that no conflict of interest exists in publishing this article.
- الموافقة الأخلاقية
- Ethics approval details were not reported in the published version of this article.
- إتاحة البيانات
- A data availability statement was not reported in the published version of this article.
المراجع (25)
14 من أصل 25 مرجعًا مرتبطة بمعرّف DOI.
- Abe, J. Yamaguchi, T. Isshiki, T; Myocardial reperfusion can be predicated by myoglobin/creatine kinase ratio of a single blood sample obtained at the time of admission. Am. Heart J., 126: 279-285, 1993. DOI Crossref PubMed Google Scholar
- Abramson, J. H; Risk markers for mortality among elderly men community study in Jerusalem, J. Chronic disease; 35: 563-572, 1982. DOI Crossref PubMed Google Scholar
- Allain CC, et al; American Heart Association; Coronary Risk Handbook. Estimating Risk of Coronary Heart Disease in daily practice. Clin Chem, 20: 470-475, 1974. PubMed Google Scholar
- Bakker, AJ; Koelemay, MW; Gorgels; J.Failure of new biochemical markers to exclude acute MI at admission Lancer, 342, 1220-2, 1993 PubMed Google Scholar
- Chapelle, J.P., Allaf, M.E; Determination of myoglobin in serum by kinetic turbidimetry using the turbitime system. Clin. Chem., 36: 1193, 1990. Ulutas Med J 2015;1(3):68-73 Mohammed AMANULLAH et al. Assessment of Acute Myocardial Infarction PubMed Google Scholar
- Drexel, H., Dworzak, E., Kirchmair, W; Myoglobinemia in the early phase of acute myocardial infarction. Am. Heart J., 105: 642-650, 1983. DOI Crossref PubMed Google Scholar
- Ellis, A. K., Little, T., Masvil, A. R. Z; Early noninvasive detection of successful reperfusion in patients with acute myocardial infarction. Circulation, 78: 1352-1357, 1988. DOI Crossref PubMed Google Scholar
- Gibler, W. B., Lewis, L. M., Erb, R. E; Early detection of acute myocardial infarction in patients presenting with chest pain and ECGs: Serial CK-MB sampling in the emergancy department. Ann. Emerg. Med., 19: 1359-1366, 1990. DOI Crossref PubMed Google Scholar
- Gibler, W.B., Gibler, C.D., Weinshenker, E; Myoglobin as an early indicator of acute myocardial infarction. Ann. Emerg. Med., 16: 851-856, 1987. PubMed Google Scholar
- Gibler, W.B., Runyon, J.P., Levy, R.C; A rapid diagnostic and treatment center for patients with chest pain in the emergency department. Ann. Emerg. Med. 25: 1-8,1995. DOI Crossref PubMed Google Scholar
- Griesmacher, A., Grimm, M., Schreiner, R., Müller, M.M; Diagnosis of preoperative myocardial infarction by considering relationship of postoperative electrocardiogram changes and enzyme increases after coronary bypass operation. Clin. Chem., 36: 883-887, 1990. DOI Crossref PubMed Google Scholar
- IFCC method for the measurement of catalytic concentration of enzyme. J Clin Chem Clin Biochem, 24: 497-510, 1986. PubMed Google Scholar
- IFCC methods for measurement of catalytic concentration of enzyme. JIFCC, 1: 130-139, 1989. PubMed Google Scholar
- Katrukha, A.G., Bereznikova, A.V., Esakova, T.V; Troponin I is released in bloodstream of patients with acute myocardial infarction not in free form but as complex. Clin. Chem., 43: 1379-1385, 1997. DOI Crossref PubMed Google Scholar
- Laperche, T., Steg, P.G., Benessiano, J; Patterns of myoglobin and MM creatine kinase isoform release early after intravenous thrombolysis or direct percutaneous transluminal coronary angioplasty for acute myocardial infarction, and implications for the early noninvasive diagnosis of reperfusion. Am. J. Cardiol., 70: 1129-1134, 1992. DOI Crossref PubMed Google Scholar
- Lee, T.H., Goldman, L; Serum enzyme assays in diagnosis of acute myocardial infarction. Ann. Intern. Med., 105: 221-233, 1986. PubMed Google Scholar
- Leung, F.T., Galbraith, L.V., Jablonsky, G., Henderson, A.R; Re-evaluation of the diagnostic utility of serum total creatine kinase and creatine kinase-2 in myocardial infarction. Clin Chem., 35: 1435-1440, 1989. DOI Crossref PubMed Google Scholar
- Lindahl. B, Venge. P, Wallentin. L; Early diagnosis and exclusion of acute Myocardial Infarction using biochemical monitoring. The BIOMACS study group, biochemical markers of acute coronory syndrome. Coron Artery Dis, 6: 321-8, 1995. DOI Crossref PubMed Google Scholar
- Collinson, L. Sylven, C., Santonyi, p; Lactate dehydrogenase and its isoenzyme activities in different parts of normal human heart. Cardiovasc. Res., 23: 601-606, 1989. DOI Crossref PubMed Google Scholar
- Mair. S, Morandell. D; Equivalent early sensitivities of Myoglobin, CK-MB, CK isoform ratios and cardiac Troponins I and T for acute MI. Clin. Chem. 41: 1266-72, 1995. PubMed Google Scholar
- Newby, L. K; Gibler, W. B. Ohman, E. M; Biochemical markers in suspected acute MI the need for early assessment. Clin. Chem. 41: 1263-5, 1995. PubMed Google Scholar
- Ravkidle, J., Nissen, H., Horder, M., Thygesen, K; Independent prognostic value of serum creatine kinase isoenzyme MB mass, cardiac troponin T and myosin light chain levels in suspected acute myocardial infarction. J. Am. Coll. Cardiol., 25: 574-581, 1995. PubMed Google Scholar
- Vaananen, H. K., Syrjala, H., Rahkila, P; Serum carbonic anhydrase III and myoglobin concentrations in acute myocardial infarction. Clin. Chem., 36: 635-638, 1990. DOI Crossref PubMed Google Scholar
- Wu, A.H.B., Gorent, T.G., Harker, C.C; Role of rapid immunoassay for urgent determinations of creatine kinase isoenzyme MB. Clin. Chem., 35: 1752-1756, 1989. PubMed Google Scholar
- Zabel M, Hohnloser, S.H., Koster, W; Analysis of creatine.kinase, CK-2, myoglobin, and troponin T time-ac0tivity curves for early assessment of coronary artery reperfusion after intravenous thrombolysis. Circulation, 87: 1542-1550, 1993. DOI Crossref PubMed Google Scholar
اقرأ النص الكامل
افتح ملف PDF هنا
جارٍ تحميل ملف PDF…
إذا لم يظهر ملف PDF هنا، استخدم زر التنزيل أعلاه.
كيف تقتبس هذه المقالة
Akasha R, Mohammed A, Syed PA, Sirageldin E, Mohammed E, Allah MG. Assessment of Acute Myocardial infarction by the use of special biochemical markers. Ulutas Med J. 2015;1(3):68-73. doi:10.5455/umj.20150416122936
Akasha, R., Mohammed, A., Syed, P. A., Sirageldin, E., Mohammed, E., & Allah, M. G. (2015). Assessment of Acute Myocardial infarction by the use of special biochemical markers. The Ulutas Medical Journal, 1(3), 68–73. https://doi.org/10.5455/umj.20150416122936
Akasha, R. et al. (2015) 'Assessment of Acute Myocardial infarction by the use of special biochemical markers', The Ulutas Medical Journal, 1(3), pp. 68–73. doi: 10.5455/umj.20150416122936.