The Ulutas Medical Journal · ISSN 2149-0430 (مطبوع), 2149-388X (إلكتروني) · https://www.ulutasmedicaljournal.com/?mno=232578
تقرير حالة · وصول مفتوح
هل (تولفاتان) في علاج (سايد) يتبع جراحة (بيتوري) اختيار صحيح؟?
ترجمة آلية للعنوان والملخص والنص الكامل. الأصل الإنجليزي
- Department of Nephrology, Ankara Training and Research Hospital ROR
الملخص
Background: Fluid and electrolyte disturbances, especially hyponatremia are common complications after potuitaryurgries. وتشكل متلازمة السرّية غير الملائمة للهرمونات المضادة للديوريات السبب الرئيسي لنقص في المستشفيات. Fluid restriction is the first step in treatment of SIADH. In rare cases vasopressin receptor inhibitors might be useful for medical treatment. عرض الحالة: In this paper, we present a case of SIADH after a crauitary wound with an unpredictable effect of tolvaptan. الاستنتاج: تولفاتان هو أكثر العوامل تفضيلاً لمعاملة الرابطة في هذه الأيام. غير أن توفاتان قد يتسبب في حالات لا يمكن التنبؤ بها أثناء العلاج التي يجب أن يكون فيها المستوصفون حذرين جدا وفي متابعة دقيقة للمريض.
الكلمات المفتاحية
النص الكامل
ترجمة آلية للنص الكامل؛ النسخة المعتمدة هي الأصل الإنجليزي. الأصل الإنجليزي
مقدمة
The state of serum sodium level less than 135 mEq/L is defined as hyponatremia. وتنجم هيبوناترميا عموما عن الاحتفاظ بمياه غير مستحقة مقارنة بفقدان الصوديوم بدلا من الصوديوم وحده. The over secretion of antidiuretic hormone (ADH) impairs the water excretion and causes hyponatremia; this disorder is named as the syndrome of inappropriate antidiuretic hormone secretion (SIADH). SIADH is the leading cause of hyponatremia in hospital settings (1).
فبعد الجراحات البدائية، تكون الاضطرابات بالكهرباء مضاعفات مشتركة، ويمكن أن يحدث النفاق بطريقة معزولة أو كجزء من نمط ثنائي أو ثلاثي. وعموماً، فإن المعهد الوطني لحقوق الإنسان، بسبب الجراحة الهزلية، لديه دورة حدية ذاتية وسيتعافى في غضون يومين ونصف (2).
In case of SIADH, therapeutic options are treatment of the underlying disease, liquid restriction, in severe cases intravenous saline and vasopressin receptor antagonists like vaptans (3)تولفاتن) يعرقل)2 Reeptors of ADH and causes to only water diuresis without sodium and potassium excretion (4)The serum sodium level will be on an upward trend by electrolyte-free water loss in SIADH patients after tolvaptan and this will improve mental state of patients with hyponatremia. وهنا نقدم حالة SIADH بعد جراحة بدائية مع تأثير لا يمكن التنبؤ به من التولفتان.
عرض الحالة
أنثى عمرها 29 عاماً مع تاريخ طبي سابق لمرض (هاشيموتو) تم قبولها في المستشفى مع صداع ومزامنة ولدى قبول المريض، كانت جميع البارامترات المختبرية في المدى العادي. وأظهرت الصورة المجمعة للرأس أن هناك آفة متينة ذات بُعد قدره 24x19x21 ملم في منطقة الصنوبر. The lesion had applied pressure on exit of third ventricule; agua ductus cerebri and caused to dilatation of third and lateral ventricules.
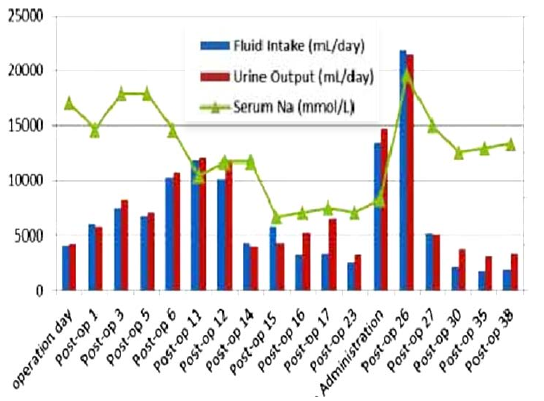
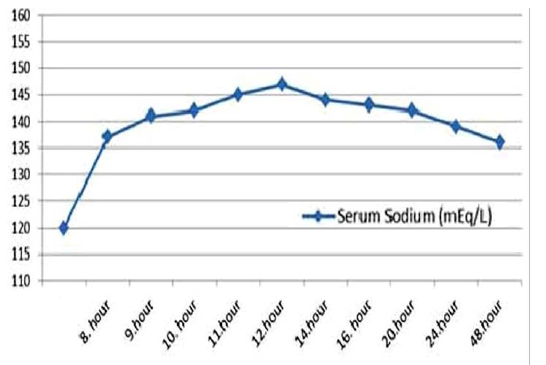
She was operated on 19th آب/أغسطس 2015. وبعد مرور أسبوعين على تشغيلها، استشارت الوحدة المعنية بعلم الأعصاب لنفاق حاد (116 ملم/لتر). فحصها البدني غير ملحوظ لم تكن هناك علامات على نضوب الحجم أو الإيديما لم يكن هناك أي مرض رئوي واضح، أو الأورام، أو عدم كفاية الكظر، أو التقيؤ. She was found to have low plasma osmolality (247 mOsm/kg H2O) and high urine osmolality (436 mOsm/kg H2O). The urinary sodium was 121 mmol/L. She reported compliance with levothyroxine and was clinically euthyroid (TSH=1.45 mIU/L). نفاقها العميق عُزي إلى SIADH. وتم فرض قيود على الثلوج، والصلين الملحي الفائق السرعة (0.3 في المائة) والغطاء العنيف بالفوروسيميد، ولم تكن مستويات الصوديوم المصل مرضية. وقد بدأ تولفاتان 15 ملغم في اليوم الخامس والعشرين بعد التشغيل بمستوى المصل من الصوديوم 120 ملليمتر/لتر (الشكل 1). After 8 hours she had a rapid increase in his serum sodium level from 120 mmol/L to 137 mmol/L after she received the first dose of tolvaptan. وزادت مستويات صوديوم مصلها من 137 ملليمتر/لتر إلى 147 ملم/لتر في 12 ساعة. وفي هذه المرحلة، توقف تولفابان. وقد تبين في الشكل 2 آثار التالفاتان على مستويات الصوديوم المصلي. وقد بدأت التصويبات السريعة بالسوائل الناقصة في الساعة الثامنة من العلاج ولم يستحدث المريض علامات على متلازمة التهاب العظام.
المناقشة
أكثر التعقيدات شيوعاً بعد الجراحة الهزلية هي خلل سائل وكهربي The incidence of hyponatremia due to transsphenoidal wound is between 2, 25%(5)- يمكن النظر إلى الهيبوناتريميا بطريقة معزولة أو كجزء من نمط ثنائي أو ثلاثي الأبعاد بعد جراحة عابرة. النمط الثلاثي نادر ومصادفة في نسبة 3.4 في المائة من المرضى وحدثت المرحلتان الأوليان في 1.1 في المائة من المرضى الذين أجروا جراحة (6)The first phase of diabetes insipidus genarally has a duration of 5 -7 days and the second phase is antidiuretic phase of SIADH(7)- في مريضنا، لوحظ النفاق بعد اسبوعين الجراحة التي تذكرنا المرحلة الثانية من العلاج Although there is no hypernatremia in the first polyuric period but in the following period low serum osmolality accompanied by high urine osmolality was observed that is compatible with SIADH. غير أن مرحلتنا الثانية تختلف إلى حد ما عن مؤشر الاستثمار الثلاثي العام لأن فترتنا الثانية قد حدثت بعد أسبوع تقريبا من الوقت المتوقع. وقد يكون النفاق المنعزل نموذجاً فرعياً من أجهزة الاستنشاق الثلاثية الكلاسيكية التي لها أيضاً ثلاث مراحل؛ الأول هو مرحلة تعددية يتبعها معهد الدراسات العليا لحقوق الإنسان، وبعد تلك المرحلة الثالثة هو التعافي أو الإصابة بمرض السكري المستمر. (8)- لم يكن هناك رد كاف على الرغم من القيود العدوانية على السوائل وغطاء القوة في علاج SIADH في مريضنا حتى أضيفت تولفاتان إلى العلاج. وللأسف، حدث ارتفاع سريع في صوديوم المصل بعد تولفاتان، وهو استجابة غير متوقعة عموما أثناء هذا النوع من العلاج، ومن المهم أن يكون خطر التهاب النسيج. Verbalis JG et al. reported that the second phase of Triphasic DI might last between 2-14 days so that it may be appropriate to use Tolvaptan if patients have symptoms of hyponatremia (9)غير أن الزيادة السريعة في مستويات الصوديوم في مريضنا بعد توليفاتن قد تعزى إلى عوامل شخصية، مثل الحساسية الفائقة للمستقبِل أو قد تكون معضلة في الجدول الزمني، لأن التولفاتان قد تضاف إلى العلاج قبل المرحلة الثالثة من الدراسة الاستقصائية، بحيث قد يكون ذلك سبباً لارتفاع صوديوم المصل بسرعة. وفي الختام، لا ينبغي للمستوصفين أن يسرعوا إلى تولفاتان لمعالجة النفاق بعد إجراء جراحة بدائية ما لم يصبح المريض أعراضا. غير أنه لا توجد بروتوكولات وخوارزميات مفصلة لإدارة النفاق بعد إجراء جراحة حفرية، ويلزم إجراء المزيد من البحوث.
الإقرارات
- مساهمات المؤلفين (CRediT)
- ساهم جميع المؤلفين بالتساوي في جميع أدوار CRediT الأربعة عشر (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- التمويل
-
Funding information was not reported in the published version of this article.
- تضارب المصالح
- The authors declare that there is no conflict of interest among the authors.
- الموافقة الأخلاقية
- Ethics approval details were not reported in the published version of this article.
- إتاحة البيانات
- A data availability statement was not reported in the published version of this article.
المراجع (9)
5 من أصل 9 مرجعًا مرتبطة بمعرّف DOI.
- Borges 1. Runkle I, Villabona C, Navarro A, Pose A, Formiga F, Tejedor A, et al. Treatment of hyponatremia induced by the syndrome of Inappropriate antidiuretic hormone secretion: a multidisciplinary algorithm. Nefrologia 2014;34 (4):439-50. PubMed Google Scholar
- Janneck M, Burkhardt T, Rotermund R, Sauer N, Flitsch J, Aberle J. Hyponatremia after trans-sphenoidal surgery. Minerva Endocrinologica 2014;39(1):27-31 PubMed Google Scholar
- Rose BD. New approach to disturbances in the plasma sodium concentration. Am J Med 1986; 81(6):1033. DOI Crossref PubMed Google Scholar
- Verbalis JG, Goldsmith SR, Greenberg A, Schrier RW, Sterns RH. Hyponatremia treatment guidelines 2007: expert panel recommendations. Am J Med 2007; 120:1. DOI Crossref PubMed Google Scholar
- Janneck M, Burkhardt T, Rotermund R, Sauer N, Flitsch J, Aberle J. Hyponatremia after trans-sphenoidal surgery. Minerva Endocrinol 2014; 39(1): 27-31. PubMed Google Scholar
- Hensen J, Henig A, Fahlbusch R, Meyer M, Boehnert M, Buchfelder M. Prevalence, predictors and patterns of postoperative polyuria and hyponatraemia in the immediate course after transsphenoidal surgery for pituitary adenomas. Clin Endocrinol (Oxf) 1999;50:431–439. DOI Crossref PubMed Google Scholar
- Loh JA, Verbalis JG. Diabetes insipidus as a complication after pituitary surgery. Nat Clin Pract Endocrinol Metab 2007;3(6):489-94. DOI Crossref PubMed Google Scholar
- Ghirardello S, Hopper N, Albanese A, Maghnie M. Diabetes insipidus in craniopharyngioma: postoperative management of water and electrolyte disorders. J Pediatr Endocrinol Metab 2006; 19: 413-21. PubMed Google Scholar
- Verbalis JG, RobinsonAG, Moses AM. Postoperative and posttraumatic diabetes insipidus. In Diabetes Insipidus in Man, Front Horm Res 1984; 13: 247 http://www.ulutasmedicaljournal.com DOI Crossref PubMed Google Scholar
اقرأ النص الكامل
افتح ملف PDF هنا
جارٍ تحميل ملف PDF…
إذا لم يظهر ملف PDF هنا، استخدم زر التنزيل أعلاه.
كيف تقتبس هذه المقالة
Karakose S, Bal AZ, Unverdi S, Duranay M. Is Tolvaptan in the Treatment of SIADH Following Pituitary Surgery a Right Choice?. Ulutas Med J. 2016;2(3):154-156. doi:10.5455/umj.20160703095035
Karakose, S., Bal, A. Z., Unverdi, S., & Duranay, M. (2016). Is Tolvaptan in the Treatment of SIADH Following Pituitary Surgery a Right Choice?. The Ulutas Medical Journal, 2(3), 154–156. https://doi.org/10.5455/umj.20160703095035
Karakose, S. et al. (2016) 'Is Tolvaptan in the Treatment of SIADH Following Pituitary Surgery a Right Choice?', The Ulutas Medical Journal, 2(3), pp. 154–156. doi: 10.5455/umj.20160703095035.