The Ulutas Medical Journal · ISSN 2149-0430 (print), 2149-388X (online) · https://www.ulutasmedicaljournal.com/?mno=220089
Case Report · Open access
A Rare But Serious Entity: Corticosteroid Allergy
- Pulmonary Medicine, Viransehir State Hospital, Sanliurfa, Turkey ROR
- Thoracic Surgery, Hitit University Corum Education and Research Hospital, Corum, Turkey ROR
Abstract
- Introduction
- Systemic steroids are usually used in pulmonary medicine practise and are potential drugs in asthma less in chronic obstructive pulmonary disease (COPD) besides potential of allergy.
- Case Presentation
- We reported a sixty five years old man who had COPD for five years. The patient was hospitalised for COPD exacerbation and was treated with antibiotherapy plus bronchodilatory drugs. On the follow up when his symtoms did not decrease methyprednisolone was started. Ten minutes after the administration swelling, itchy and papuler skin lesions were observed all over the body particularly on the forearms. The patient was hospitalised a few times in the same clinic and was treated with methyprednisolone several times before but he had not experienced such a situation. Urticeria is charecterised with browned, swelling, itchy, edematous and papular lesions which tend to diseppear within 1-2 hours.
- Conclusion
- Corticosteroids seem to be rare causes of immediate hypersensitivity reactions which can be misdiagnosed. Physicians should be carefull and identify safe alternative preparations if needed.
Keywords
Full text
Introduction
Systemic steroids are usually used in pulmonary medicine practise which are potential drugs in asthma less in Chronic Obstructive Pulmonary Disease (COPD) besides rare potential of allergy and more common other side effects.
Corticosteroids may cause both immediate and delayed allergic reactions. Among these, delayed reactions to topical steroids are common whereas immediate reactions to systemic steroids are rare. There are case reports about immediate reaction to systemic cortico-steroids (1, 2). Methylprednisolone and hydrocortisone are the most commonly implicated corticosteroids in systemic use. Here we report a sixty five years old man who had COPD for 5 years. This case report is one of those rarely seen immadiate hypersensitivity reactions to corticosteroids.
Case Presentation
A sixty five years old man was admitted to our clinic with complaints of cough, dyspnea and purulant sputum. His physical examination revealed normal body temperature (36 C°), heart rate of 85 beats per minute, respiratory rate of 20 breaths per minute, blood pressure of 110/80 mm Hg, and SpO2 of 85%on room air. Physical examination of the chest revealed ronchi in all lung fields. The patient was hospitalised for COPD exacerbation and was treated with antibiotherapy plus bronchodilatory drugs. On the follow up when his symtoms did not decrease methyprednisolone was administered. Ten minutes after the administiration swelling, itchy and papuler skin lesions was observed (Picture-1).
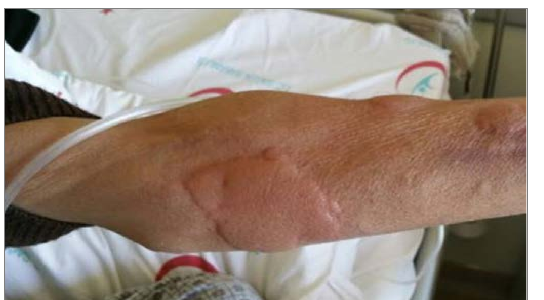
Lesians disppeared spontaneously a few minutes later. The patient was hospitalised a few times in the same clinic and was treated with methyl-prednisolone several times before, but such a reaction did not observed before.
Discussion
Urticeria is charecterised with browned, swelling, itchy edematous and papular lesions which tend to diseppear within 1-2 hours. The incidence of corticosteroid allergy is unkown but it is probably more common than reported. In patients using multiple therapies most cases of corticosteroid allergies are usually misdiagnosed.
Recognizing corticosteroid allergy can be difficult, because its non-specific clinical presentation and the clinical signs are usually minor, or display a completely atypical chronology, which is due to the anti-inflammatory properties of the corticosteroids. The entity can occur in any age and gender (3). Skin testing may provide sufficient evidence to diagnose allergy in patients with a clear history of immediate hypersensitivity to corticosteroids (4). But in those who has no previous history it is difficult to put the diagnosis as was in our case.
Our patient was a sixty five years old man who had been on follow up for COPD and had used methyprednisolone for many times but had not experienced allergic reaction before. It is therefore difficult to forsee the reaction. There is limited data in the literature, De sousza et al described 5 cases (3) Venturini et al described 7 cases of immediate-type reactions to systemic corticosteroids (5).
In conclusion corticosteroids are rare causes of immediate hypersensitivity reactions which can be misdagnosed. Corticosteroids should be included in differential diagnosis in patients who develop an allergic reaction during medication. Physicians should be carefull and identify safe alternative treatment modalities if needed.
Declarations
- Author contributions (CRediT)
- All authors contributed equally to all 14 CRediT roles (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- Funding
-
Funding information was not reported in the published version of this article.
- Conflicts of interest
- A conflict of interest statement was not reported in the published version of this article.
- Ethics approval
- Ethics approval details were not reported in the published version of this article.
- Data availability
- A data availability statement was not reported in the published version of this article.
References (5)
3 of 5 references are linked to their DOI.
- Kamm GL, Hagmeyer KO. Allergic-type reactions to corticosteroids. Ann Pharmacother 1999; 33: 451-460. DOI Crossref PubMed Google Scholar
- Kim SH. Anaphylaxis induced by oral methylprednisolone in a 10-year-old boy. Pediatr Int 2014; 56: 783-784. DOI Crossref PubMed Google Scholar
- de Sousa NG, Santa -Marta C, Morais- Almeida M. Systemic corticosteroid hypersensitivity in children. J Investig Allergol Clin Immunol 2011; 20: 529-532. PubMed Google Scholar
- Baker A, Empson M, The R, Fitzharris P. Skin testing for immediate hypersensitivity to corticosteroids: a case series and literature review. Clin Exp Allergy 2014;45: 669-676. DOI Crossref PubMed Google Scholar
- Venturini M, Lobera T, del Pozo MD, Gonzalez I, Blasco A. Immediate hypersensitivity to corticosteroids. J Investig Allergol Clin Immunol 2006; 16: 51-56. PubMed Google Scholar
Respond to this article
Comments on a published article are welcome as a Letter to the Editor.
Get an e-mail when new articles in your fields are published
Questions to the authors
Questions are moderated: an editor approves each question, the authors answer, and an editor approves the answer before both appear here.
No answered questions yet.
Ask the authors a question
Discussion
Comments are moderated: they appear after the writer confirms the e-mail address and an editor approves them. Each comment carries a conflict-of-interest statement.
No comments yet.
Write a comment
Read the full text
Open the PDF here
Loading the PDF…
If the PDF does not show here, use the download button above.
How to cite this article
Koc I, Ulusan A. A Rare But Serious Entity: Corticosteroid Allergy. Ulutas Med J. 2016;2(2):130-131. doi:10.5455/umj.20160413123602
Koc, I., & Ulusan, A. (2016). A Rare But Serious Entity: Corticosteroid Allergy. The Ulutas Medical Journal, 2(2), 130–131. https://doi.org/10.5455/umj.20160413123602
Koc, I. and Ulusan, A. (2016) 'A Rare But Serious Entity: Corticosteroid Allergy', The Ulutas Medical Journal, 2(2), pp. 130–131. doi: 10.5455/umj.20160413123602.