The Ulutas Medical Journal · ISSN 2149-0430 (print), 2149-388X (online) · https://www.ulutasmedicaljournal.com/?mno=246501
Original Article · Open access
Brain Imaging Assessment of Associated Abnormalities in Patients with Cavum Septi Pellucidi
Also available in: العربية · Türkçe · 中文
- Radiologist specialist, Section of Radiology, Department of Surgery, Al-Nahrain College of Medicine, University of Al-Nahrain, Baghdad, Iraq ROR
- Radiologist specialist, Section of Radiology, Department of Surgery, Al-kindy College of Medicine, Baghdad University, Baghdad, Iraq ROR
Abstract
- Introduction
- Cavum septi pellucidi (CSP) describes a septum pellucidum that has a separation between its two leaflets and contains cerebrospinal fluid. Multiple studies was held previously to evaluate the CSP and some of those studies consider it as a normal variant while the other consider it as a sign of midline brain developmental abnormality. The objective of our study was to assess the relation of CSP to other brain abnormalities and correlate this to its size and form of presentation.
- Methods
- We reviewed the neuroimaging studies of 1840 patients in our cross sectional study. A CSP was found in 85 (4.6%) of these patients. We graded CSP into three grades: I <1 cm3, II 1-2 cm3, III >2 cm3.
- Results
- Headache was the main presenting symptom in 44.7% of our patients sample (P<0.001). Patients less than 20 years old tend to have grade I CSP while grades II and III occurred more in patients older than 20 (P<0.001). 67.8% of patients with grade I show no associated brain abnormality Conclusion: There is no significant predominance of one sex over the other to have CSP. Grade I was noted more in patients less than 20, some of them presented with developmental delay and seizures. Grades II and III were more common in patients older than 20, some of them presented with past history of tumors. Most of grade I patients show no other abnormality while most of patients with grades II and III show other abnormalities in their brain imaging.
Keywords
Full text
Introduction
The cavum septi pellucidi (CSP) is the space between the two leaflets of the septum pellucidum (1). Examples of CSP can be seen in Figure-1. The septum pellucidum is a thin triangular translucent sheet of two laminae that extends from the anterior part of the body, the genu, and the rostrum of the corpus callosum to the superior surface of the fornix. During fetal development at approximately the twelfth week of gestation, a space forms between two laminae, which is the CSP. At approximately the twentieth week of gestation, the laminae start to close. This closure ends shortly after birth (3–6 months postnatally) in ninety per cent of cases (1, 2). Fusion of the CSP is attributed to rapid development of the hippocampus and corpus callosum. Incomplete fusion results in the persistence of a cavum, which, in turn, reflects possible neurodevelopmental anomalies of these midline structures (2).
CSP is sometimes called the fifth ventricle but this term seems to be inappropriate as there is no any direct communication with the ventricular system. CSP has been loosely associated with schizophrenia, post-traumatic stress disorder, chronic brain trauma and antisocial personality disorder (3–5). An absent CSP in antenatal imaging is a concerning feature and is associated with significant CNS anomalies (6). However, for the majority of individuals, CSP produces no ill effects.
Multiple studies was held previously to evaluate the CSP and some of those studies consider it as a normal variant while the other consider it as a sign of midline brain developmental abnormality. The purpose of this study was to assess the relation of CSP to other brain abnormalities and correlate this to its size and form of presentation.
Study Design
Between May 2014 and 2016, we reviewed 1840 brain imaging requested patients ranging in age from 3 months till 65 years in medical city hospitals, Baghdad, Iraq. Patients were presented with different signs and symptoms subjected them for brain magnetic resonance imaging (MRI) and multidetectors computed tomography (MDCT) imaging. A CSP was found in 85 (4.6%) of these patients;41 (48.2%) were female and 44 (51.8%) were male. Each patient included in this cross sectional study underwent a review of their request for brain imaging with their presenting symptoms and clinical data. The measurements is taken in three dimensions to measure the size of the CSP and according to the results, we graded CSP into three grades: I<1 cm3, II:1-2 cm3, III>2 cm .
Approval of our institutional ethical committee was taken before beginning of this study. Informed consent was not obtained from individual participants included in this cross sectional study as no patient data will appear in this manuscript. Modalities used for patients brain imaging evaluation were MRI and MDCT. Regarding the MRI, all scans were performed on a General Electric 1.5 Tesla scanner. The images were reformatted in the coronal plane, with 1-mm thickness, and consisted of 128 contiguous slices. The axis for coronal slices was parallel to the axis of the brainstem. Coronal sequences extended from the tip of the frontal pole to the tip of the occipital pole. Regarding CT scan, all scans were performed on a General Electric 64 slices MDCT scanner. acquisition parameters were as follows: head scan FOV scan type: Helical, Rotation Time: 0.4 sec, beam collimation (mm): 20mm, 16 detector rows, pitch=0.531, speed=10.62 mm/rotation, slice thickness=2.5mm, interval =1.25 mm, kV=120. Images reconstruction was done in two windows; brain soft tissue (WW=80, WL=25) and bone (WW=3000, WL=300). The patients head tilt so that a line connecting the lateral canthus of the eye and the external auditory canal is perpendicular to the CT table top. We used axial mode and angle the gantry when we cannot place the patient’s head within 15 degrees of the proper setup angle. These images were reconstructed in the coronal plane, with 0.6 mm thickness; the axis for coronal slices was parallel to the axis of the brainstem.
Data management and statistical analysis were performed by using the statistical package for social sciences (SPSS) version 19 for Microsoft Windows. Statistical significance was indicated by a p value of less than 0.05.
Results
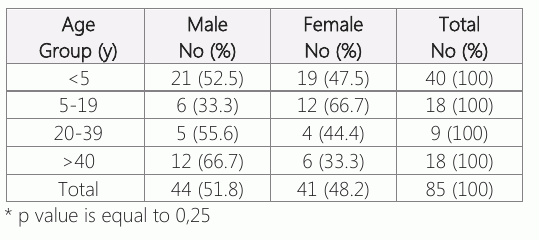
Males constitute 51.8% of our patient's sample while 48.2% of them were females, so in our sample male: female ratio was 1.07:1. This slight male predominance was noticed in all age groups that had been studied except in those young children and teenagers, i.e. 5-19 years old, but these findings were not significance (p:0.25) as seen in Table-1.
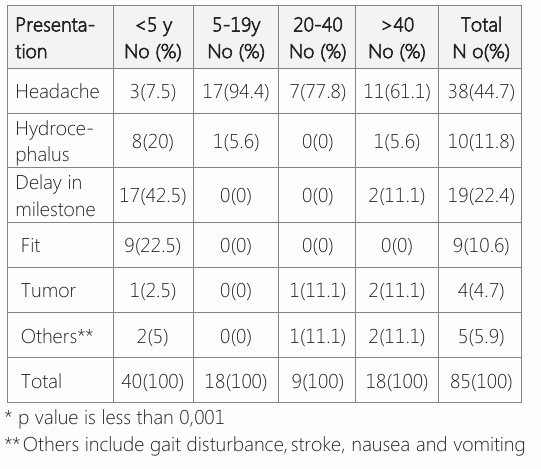
Headache comprise 44.7% of our patients sample presentation; it was the main presenting symptom in 94.4% of age group 5-19 year old and 77.8% of age group 20-40 year old, while delayed in milestones was the main presenting symptom in 42.4% of age group below 5 year old as seen in Table-2 in which the results were significant (p<0.001).
Our results show that the first presented symptom in both sex was headache (45.9%) with slight female predominance while the second was delayed in milestone (20%) with male predominance (p:0.75). According to the measurements for the size of CSP in our patients sample, we graded CSP into three grades: I<1 cm3, II:1-2 cm , III>2 cm ). We found that 75.6% of the female patients presented with small size CSP (grade I) while large size CSP (grades II and III) tend to present more in males (p:0.405).
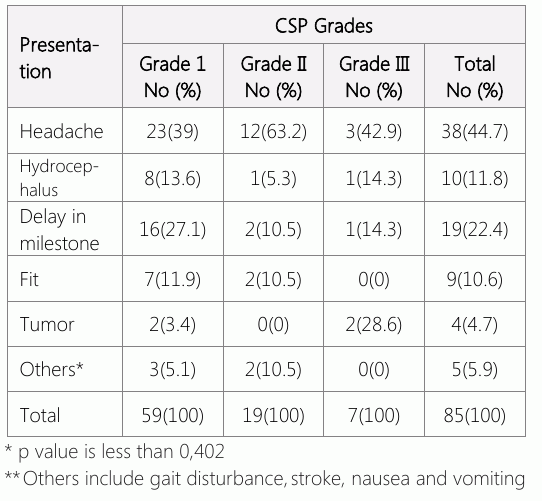
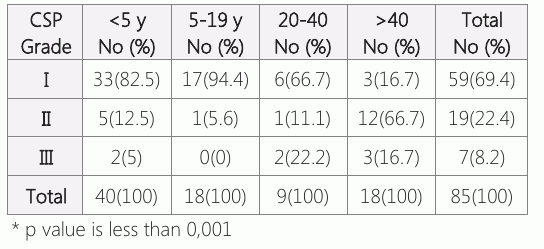
As in Table-3, our results show significant predominance of grade I CSP in patients less than 20 year old and grades II and III in patients more than 20 year old (p<0.001). Our results show that there is not significant association between tumors (28.6%) as past presenting complain and grade III CSP. Most of grade II CSP patients presented with headache (63.2%) while only 39% of grade I CSP patients presented with headache as in Table-4 (p:0.402).
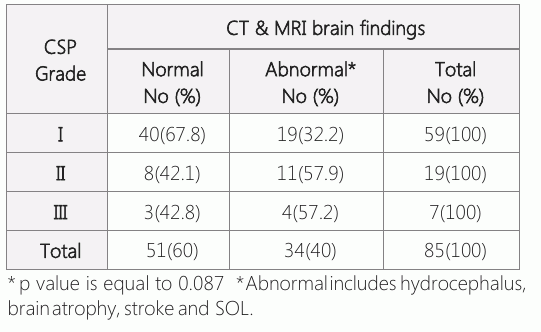
Although the results are not significant (p:0.087), 67.8% of patients with grade-I CSP show no associated brain abnormality while 57.9% of patients with grade-II & 57.2% of patients with grade-III CSP show other associated abnormalities in their brain imaging as seen in Table-5.
Discussion
Multiple studies was held previously to evaluate the CSP and most of them concentrate on infants and few focus on the relation between its present and certain psychological disorders.
In our study, the incidence of CSP was 4.7% and there was no significant predominance of one sex over the other to have it; however grade II and III tend to presented more in males than females. This percentage was approximately comparable to that registered by Nakano S, et al (7) in 1981 who reported that CSP were present in 5.5 of children brains and approximately three folds lower than that registered by Mapstone TB, et al also in 1981 who showed that CSP are present in approximately 15% of adult brains (8). In 1983, Akiyama K, et al (9) publish that seventy one patients with CSP were found among 2722 patients who had received CT scanning at a mental hospital. In this study, the incidence of CSP was 2.6%, sex ratio was M:F 1.9:1 which are a results close to ours.
In Nakano S, et al study (7) an attempt was made to assess possible relationships between clinical syndromes (convulsive disorders, developmental delays, and others) and the presence of CSP. No solid statistical evidence of such relationships could be established. In Akiyama K et al study (9), complications of epileptic attacks and mental retardation were 22.5% and 9.9% of the patients with CSP, respectively. Frequency of these complications was significantly higher, as compared with the patients without CSP. Bodensteiner JB, et al (10) in 1990 found that eight out of nine children studied showed observed abnormalities included cognitive impairment, seizures, hypoplasia of the corpus callosum, optic nerve hypoplasia, and growth failure.
The incidence of intellectual dysfunction, the association with midline anomalies of the brain, and growth failure all suggest that wide CSP may represent part of a spectrum of midline brain anomalies. Similar findings were noticed in 1998 by Guru Raj AK, et al (11) who detect fifty four con-secutive cases of CSP amongst 1281 patients who underwent cranial CT scans; and their clinical and radiological features were studied. Recurrent seizures and developmental delay were the commonest presenting symptoms seen. Significant neurological deficits were present in 75.9% of these cases. Additional cerebral abnormalities were observed in the CT scan in 76% of cases, the commonest being cortical atrophy, cerebral infarction and hydrocephalus. Similarly in 2007, Kaciński M, et al (12) reported that the majority of the children with CSP had also coexisting brain malformations diagnosed in MRI e.g. dysplasia septo-optica and agenesis of corpus callosum.
Mental retardation was diagnosed in 1/3 children with different structural brain malformation but also in 11% of children with CSP as well. Comparatively our results shows that headache was the main presenting symptoms in all age groups and, although the results were not significant, 67.8% of patients with grade I CSP show no associated brain abnormality while 57.9% of patients with grades II & 57.2% of patients with grade III CSP show other associated abnormalities in their brain imaging. In 1996, Shioiri T, et al (13) studied 113 patients with affective disorders (69 with bipolar disorder and 44 with major depression), 40 schizophrenic patients, and 92 control subjects by MRI. Significantly higher incidence of CSP (moderate to large) compared with the controls was found only in schizophrenics. These findings are consistent with the hypothesis that neurodevelopment abnormality may be present in schizophrenia, and such an abnormality may also be present in some patients with bipolar disorder. Also in 1996, Nopoulos P, et al (14) stated that CSP is a midline developmental anomaly shown to have increased incidence in patients with schizophrenia.
In 2003, Kim KJ, et al (15) noticed that CSP size in tuberous sclerosis (TS) children was significantly smaller than in normal control subjects, and it was inversely associated with attention-deficit/hyperactivity disorder (ADHD) symptom severity in the TS subjects. CSP size was not significantly associated with the comorbid diagnoses of obsessive-compulsive disorder (OCD) or ADHD. These results were replicated in the independent sample of adults with TS and their same-age control subjects. In 2004, Galarza M, et al.3 published that thirtytwo female patients with a diagnosis of residual schizophrenia and 19 female control subjects were studied through cerebral MRI. The prevalence of CSP was significantly higher in the patients with schizophrenia. No other significant associations with previously described morphological brain changes were found. As our study was held in a general hospital (not in a mental hospital), no schizophrenic patients were included.
Conclusion
Our study reviewed 1840 brain imaging requested patients and CSP was found in 85 (4.6%) of them. There is no significant predominance of one sex over the other to have CSP however grade II and III CSP tend to presented more in males than females. Grade I CSP was noted more in patients less than 20 year old, some of them presented with developmental delay and seizures.
Grades II and III CSP were more common in patients older than 20 year old, some of them pre-sented with past history of tumors. Although the results are not significant but most of grade I CSP patients show no other abnor-mality while most of patients with grades II and III CSP show other abnormalities in their brain imaging.
Declarations
- Author contributions (CRediT)
- All authors contributed equally to all 14 CRediT roles (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- Funding
-
Funding information was not reported in the published version of this article.
- Conflicts of interest
- No conflict of interest has been declared by the authors who joined the current article.
- Ethics approval
- The measurements is taken in three dimensions to measure the size of the CSP and according to the results, we graded CSP into three grades: I<1 cm 3 , II:1-2 cm 3 , III>2 cm 3 . Approval of our institutional ethical committee was taken before beginning of this study.
- Data availability
- A data availability statement was not reported in the published version of this article.
References (15)
11 of 15 references are linked to their DOI.
- Borges TP, Kurebayashi LFS, Silva MJPD. Occupational low David L. Clark, Nash N. Boutros, Mario F. Mendez. The brain and behavior: An introduction to behavioral neuroanatomy. 3 rd ed. Cambridge: Cambridge University Press 2010.pp. 217– 8. DOI Crossref PubMed Google Scholar
- Raine A; Lee L; Yang Y; Colletti P. Neurodevelopmental marker for limbic maldevelopment in antisocial personality disorder and psychopath. Br J Psychiatry 2010;197:186– 92. Brain Imaging Assessment of Cavum Septi Pellucidi KHUDHAIR AL-SAEDI, et al. DOI Crossref PubMed Google Scholar
- Galarza M, Merlo AB, Ingratta A, Albanese EF, Albanese AM. Cavum septum pellucidum and its increased prevalen-ce in schizophrenia: a neuroembryological classification. J Neuropsychiatry Clin Neurosci 2004;16:41-6. DOI Crossref PubMed Google Scholar
- May FS, Chen QC, Gilbertson MW, Shenton ME, Pitman RK. Cavum septum pellucidum in monozygotic twins discordant for combat exposure: relationship to post traumatic stress disorder. Biol Psychiatry 2004;55:656-8. DOI Crossref PubMed Google Scholar
- Zhang L, Ravdin LD, Relkin N, Zimmerman RD, Jordan B, Lathan WE. Increased diffusion in the brain of professional boxers: a preclinical sign of traumatic brain injury? AJNR Am J Neuroradiol 2003;24:52-7. PubMed Google Scholar
- Winter TC, Kennedy AM, Byrne J, Woodward PJ. The cavum septi pellucidi: why is it important? J Ultrasound Med 2010;29:427-44. DOI Crossref PubMed Google Scholar
- Nakano S, Hojo H, Kataoka K, Yamasaki S. Age related incidence of cavum septi pellucidi and cavum vergae on CT scans of pediatric patients. J Comput Assist Tomogr 1981;5: 348-9. DOI Crossref PubMed Google Scholar
- Mapstone TB, White RJ. Cavum septi pellucidi as a cause of shunt dysfunction. Surg Neurol 1981;16:96-8. DOI Crossref PubMed Google Scholar
- Akiyama K, Sato M, Sora I, Otsuki S, Wake A, Fukui H, et al. A study of incidence and symptoms in 71 patients with cavum septi pellucidi. No To Shinkei 1983;35:575-81. PubMed Google Scholar
- Bodensteiner JB, Schaefer GB. Wide cavum septum pellucidum: a marker of disturbed brain development. Pediatr Neurol 1990;6:391-4. DOI Crossref PubMed Google Scholar
- Guru Raj AK, Pratap RC, Jayakumar R, Ariffin WA. Clinical features and associated radiological abnormalities in 54 patients with cavum septi pellucidi. Med J Malaysia 1998;53:251-6. PubMed Google Scholar
- Kaciński M, Kubik A, Herman-Sucharska I, Paciorek A, Kroczka S, Zajac A. MRI brain imaging data in children with cavum septi pellucidi and vergae. Przegl Lek 2007;64:923-8. PubMed Google Scholar
- Shioiri T, Oshitani Y, Kato T, Murashita J, Hamakawa H, Inubushi T, et al. Prevalence of cavum septum pellucidum detected by MRI in patients with bipolar disorder, major depression and schizophrenia. Psychol Med 1996;26:431-4. DOI Crossref PubMed Google Scholar
- Nopoulos P, Swayze V, Andreasen NC. Patter n of brain morphology in patients with schizophrenia and large cavum septi pellucid. J Neuropsychiatry Clin Neurosci 1996;8:147-52. DOI Crossref PubMed Google Scholar
- Kim KJ, Peterson BS. Cavum septi pellucidi in Tourette syndrome. Biol Psychiatry 2003;54:76-85. DOI Crossref PubMed Google Scholar
Respond to this article
Comments on a published article are welcome as a Letter to the Editor.
Get an e-mail when new articles in your fields are published
Questions to the authors
Questions are moderated: an editor approves each question, the authors answer, and an editor approves the answer before both appear here.
No answered questions yet.
Ask the authors a question
Discussion
Comments are moderated: they appear after the writer confirms the e-mail address and an editor approves them. Each comment carries a conflict-of-interest statement.
No comments yet.
Write a comment
Read the full text
Open the PDF here
Loading the PDF…
If the PDF does not show here, use the download button above.
How to cite this article
Al-Saedi WAK, Hassan QA. Brain Imaging Assessment of Associated Abnormalities in Patients with Cavum Septi Pellucidi. Ulutas Med J. 2016;2(3):148-153. doi:10.5455/umj.20161103024551
Al-Saedi, W. A. K., & Hassan, Q. A. (2016). Brain Imaging Assessment of Associated Abnormalities in Patients with Cavum Septi Pellucidi. The Ulutas Medical Journal, 2(3), 148–153. https://doi.org/10.5455/umj.20161103024551
Al-Saedi, W.A.K. and Hassan, Q.A. (2016) 'Brain Imaging Assessment of Associated Abnormalities in Patients with Cavum Septi Pellucidi', The Ulutas Medical Journal, 2(3), pp. 148–153. doi: 10.5455/umj.20161103024551.
@article{umj246501,
  title = {Brain Imaging Assessment of Associated Abnormalities in Patients with Cavum Septi Pellucidi},
  author = {Al-Saedi, Wassan A Khudhair and Hassan, Qays A},
  journal = {The Ulutas Medical Journal},
  year = {2016},
  volume = {2},
  number = {3},
  pages = {148--153},
  doi = {10.5455/umj.20161103024551},
  url = {https://www.ulutasmedicaljournal.com/?mno=246501},
  issn = {2149-388X}
}