The Ulutas Medical Journal · ISSN 2149-0430 (print), 2149-388X (online) · https://www.ulutasmedicaljournal.com/?mno=216539
Original Research · Open access
Do Patients Perform Their Exercises at Home and why (not)? A Survey on Patient Habits during Rehabilitation Exercises
- Laboratory of Anatomy, Biomechanics and Organogenesis (LABO), Université Libre de Bruxelles, CP 610, Lennik Street 808, 1070 Brussels, Belgium ROR
- Department of Electronics and Informatics - ETRO, Vrije Universiteit Brussel, Pleinlaan 2, B-1050 Brussels, Belgium ROR
Abstract
- Introduction
- The aim of this paper is to quantify the participation of patients during at-home exercises and also to understand why patients are not performing these exercises, which are nevertheless a major component of the rehabilitation and find some perspectives to increase patients motivation and participation. Material and method: A self-reporting survey was conducted. 319 patients (mean age≤42±15 years old, 147 female) having experience with the different specialty of physiotherapy participated in this study. The main outcome measure is the percentage of adherence to at-home exercises. Secondary outcomes of measurement are reasons why patients are not performing these exercises and finally what could stimulate them to do it.
- Results
- 29% of the patients reports in a total adherence, 54% are partially adherence and 17% of the patients do not perform any of the recommended exercises. Partially mean that patients only performed 33% of the right amount of repetitions and duration. The total percentage of participation is about 50% of the recommendation of physiotherapists. Lack of time and tedious exercises are the two main reasons why patients do not do these exercises.
- Conclusion
- Guidelines recommend the use of exercises program as a supplement of physiotherapy sessions. However, patient participation and adherence are quite low. Therefore specific solution must be developed to increase patient motivation and in fine the quality of treatment and care.
Keywords
Full text
Introduction
In rehabilitation, most of the time, the success of physiotherapy programs is reliant on patients undertaking specific exercises at home. Indeed lots of clinical guidelines for musculoskeletal disorders recommend the use of exercises program for specific pathologies [e.g. neck pain (1), osteoarthritis (2)] but also for chronic pain (3). A prerequisite for the success of these exercises is, of course, the correct realization of those one. Therefore the adherence to home exercises defined as “the extent to which a person’s behavior corresponds with agreed recommendations from a healthcare provider” (4) is a major point for the success of the rehabilitation. The problem of non-adherence to treatment does not only concern home exercises but also the rehabilitation session with the physiotherapist; according the various studies it is indeed estimated that only between 44% and 85% of the patients completed the full course of physiotherapy (5, 6). Although some scales have been developed to assess adherence to home-based rehabilitation exercises, it appears that it is difficult to get reliable results about patients’ adherence (7). There are quite variable numbers found in the literature ranging from 13% (8) up to 40 to 60% (7–9) of non-adherence rate. In practice patients have, most of the time, a set of exercises that they have to perform regularly (the frequency is depending on the severity of the disease). Patients are considered as non-adherent if they do not perform any of these exercises and adherent if they fully achieved it (7).
Actually this dualistic approach is too restrictive and a distinction must be performed between non-adherent, partially adherent and highly adherent (10). These authors found that 35% were highly adherent, 41% partially adherent and the 24% remaining non-adherent (10). There is still, currently, a lack of information about percentage of adherence to treatment and especially the amount of exercises that are really performed by the patients. Therefore the aim of this paper was to quantify the participation of patients during at-home exercises but also and to understand why patients are not performing these exercises, which are nevertheless a major component of the rehabilitation, and discuss some perspectives to increase the patients’ motivation and participation.
Materials and methods
Questionnaire
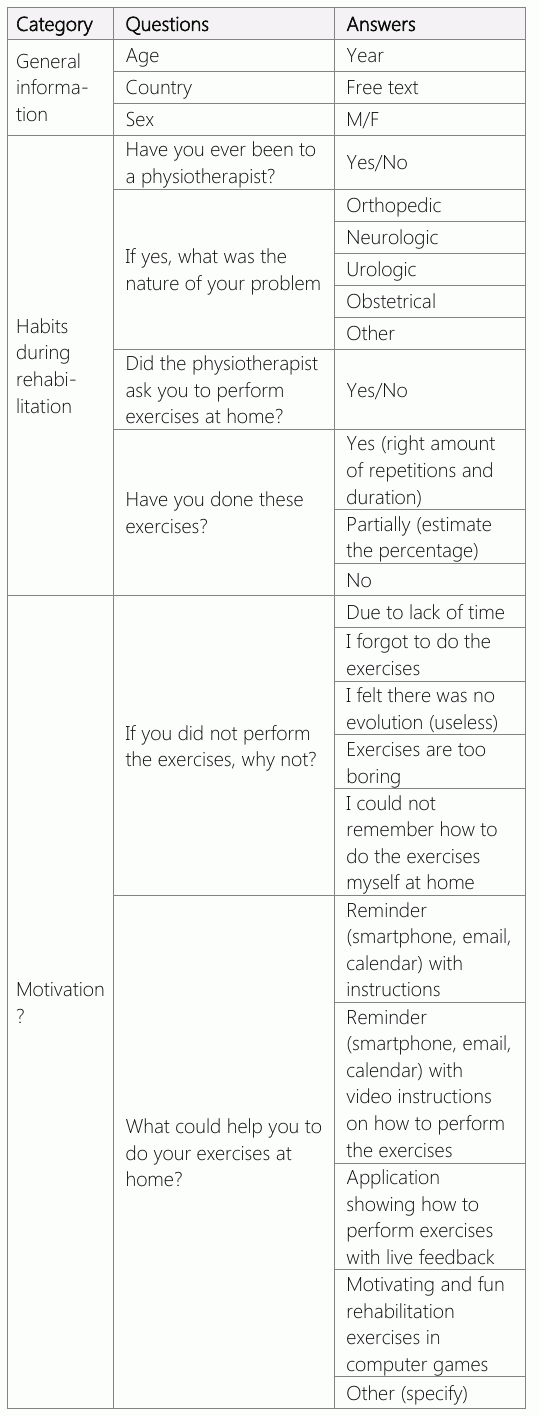
A questionnaire of nine questions was created. This questionnaire is presented in Table-1. It has been translated in French, Dutch, German, Italian, Spanish, Portuguese, Slovak and Russian. The questionnaire was distributed thought the Internet. The questionnaire is separated into three parts: one about general information, one about the rehabilitation sessions (including at-home exercises) and the last one about motivation of doing or not doing the exercises.
Population
A total of 319 patients [mean age:42±15 years old (min:20, max:81), 147 female] from 15 countries (Belgium (n:99, 31%), United- States of America (n:76, 23.8%), Slovakia (n:64, 20%), Italy (n:24, 4.7%), Spain (n:15, 4.7%), France (n:12, 3.7%), Russia (n:12, 3.7%), Portugal (n:5, 1.6%), Luxembourg (n:3, 0.9%), United-Kingdom (n:3, 0.9%), Germany (n:2, 0.6%), Equator (n:1, 0.3%), Switzerland (n:1, 0.3%), Brazil (n:1, 0.3%) and India (n:1, 0.3%) participated in this survey. Only participants who have already been to physiotherapist once in their lives were included in this study.
Statistical analysis
Descriptive statistics and percentage were used to present the results. To quantify the adherence to treatment the percentage of participation (100% for “yes”; percentage indicated by patients for “partially” and 0% for “no”) was computed.
Results
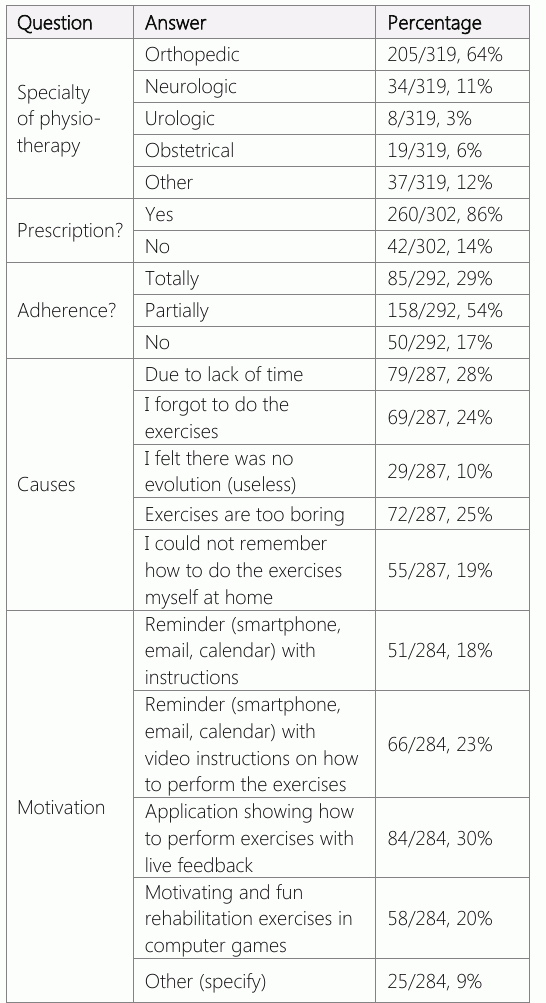
All results are presented in Table-2. For the question about adherence to treatment (question 3 in table-2) the mean percentage was 33 (30) % of performing the right amount of repetitions and duration when patients performed partially all their exercises. The total percentage of the participation rate is 48%.
Discussion
Prior to discuss of the participation of patients in home exercises the first thing to verify is whether or not physiotherapists prescribe and recommend exercises to their patients. The majority of the patients (74%) included in this study consulted physiotherapists for orthopedic disorders. Guidelines of physiotherapy and manual therapy for both acute and chronic pain (1–3) recommend the prescription of exercises to be performed at-home. Despite these recommendations it appears that 14% of the patients did not receive any exercises to do at home. No difference in term of prescription of exercises was found between the different specialties of physiotherapy.
Concerning the realization rate of these exercises by patients results of this study are in the same range of magnitude as those found in previous study (10). These authors found that 35% of the patients were highly adherent, 41% partially adherent and the 24% remaining non-adherent, our results indicate 29% of total adherence, 54% of partially and 17% of the patients that do not performed any of their exercises at-home. In the aforementioned study no information was given about the notion of partially adherent. We quantify this notion, patients that performed partially their exercises estimate that they only make about one third (33%) of the total amount of exercises recommended by physiotherapist. The total percentage of participation (taking into account the totally and the not at all adherent patients) is about the half (48%) of the prescribed exercises.
In our study we do not specify the duration of exercises while some authors did a distinction between short-term and long-term compliance (11). Without surprise the participation rate is less and less important the longer is the treatment. The authors observed a decrease of 30 to 50% of the participation within the first 12 months and between 45 and 80% within 48 months (11). It is interesting to note that the same percentages are observed with patients undergoing clinical research protocol (9) or retrospective study (7–11). This can affect negatively results of the treatment of chronic disease but it will also induce an increase of risk of relapse since some of these exercises are given to patients as a preventive measure (12).
In order to try to find solution to this problem an important point is to understand why patients do not performed the exercises. There is no trend that clearly emerges between a lack of time (28%), the boring aspect of exercises (25%) or simply due to the fact that patients forgot to do the exercises (24%). About one fifth (19%) of the patients do not remember how to correctly realize the exercises this highlights the fact that patients’ education and training is a prerequisite for the success of such kind of intervention. Luckily only one out of ten (10%) patient felt that exercises are useless. Actually except for these patients and for patients that do not have time (or find time) to perform their exercises (38% of sample) solutions currently exist or are in development to address these problems.
One of the potential negative aspect of at-home exercises is that the exercises are by definition not supervised by a healthcare specialist. In this case therapist cannot be sure that patients are performing the exercises and patients are not sure to perform them correctly. In the worst case scenario if patients do not performed the exercises in the right way (e.g. compensatory motion, wrong posture…) some counter-productive effect can even be achieved. Therefore patients are demanding for solutions allowing them to receive instruction on how to correctly realize the exercises and remind them when and how much they have to perform them (23% want to receive video instructions and 18% by text). Since a few years affordable devices (e.g. gyroscopes and accelerometers, gloves with sensors, Kinect™ sensor) are available to track specific motions and monitor follow up of the patients. About one third (30%) of the patients are requesting such kind of solution to track motions and be sure that there are correctly done. These solutions also offer more opportunity to motivate patients. Indeed the therapeutic exercises are often considered boring by patients, in order to tackle this aspect a new trend in rehabilitation is to “hide” these exercises within serious games (also called exergames) to simulate patients to do them. 20% of the patients are asking for such kind of solutions, therefore development of this new branch of physical rehabilitation should be encouraged since it appears that it can induce increase motivation of patients suffering from various diseases such as brain stroke (13), cerebral palsy (14) of for elderly people (15).
A recent Cochrane review on interventions to improve adherence to exercises studied different ways of delivering exercises on patients’ adherence (16). Main findings of this study is that supervised exercise was found to be more effective than unsupervised/home exercise at increasing exercise adherence and the accuracy of exercise performance (ie the extent to which participants perform the exercises correctly) and adherence may be improved by refresher or follow-up sessions and supplementing face-to-face instruction with other material such as an audiotape or videotape of the exercises (16). It appears thus that tele monitoring and telerehabilitation techniques could be an interesting solution to increase adherence and to increase the quality of these exercises and therefore in fine enhance the rehabilitation process. At-home exercises remain an issue in physiotherapy. Clinicians should be aware of the low participation of the patients. Indeed only 50% of the recommended exercises are really performed by the patients. However, at-home exercises are a key pieces of physical rehabilitation. Yet solution exist to increase patients participations from simple one (written instruction) to more complex one (automatic reminder with video instruction). Another challenge is to be sure that patients correctly performed their exercises. Thanks to the evolution of technology some system are developed to monitor patients at-home and provide them live feedback during the rehabilitation exercises, such kind of system seems to be well accepted by users. This could be a solution to reassure patients by correcting the realization of exercises and therapist who could control what the patients is really doing at-home.
Declarations
- Author contributions (CRediT)
- All authors contributed equally to all 14 CRediT roles (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- Funding
-
This project is funded by Innoviris (Brussels Capital Region).
- Conflicts of interest
- The authors declare no conflicts of interest.
- Ethics approval
- Ethics approval details were not reported in the published version of this article.
- Data availability
- A data availability statement was not reported in the published version of this article.
References (16)
13 of 16 references are linked to their DOI.
- Childs JD, Cleland JA, Elliott JM, Teyhen DS, Wainner RS, Whitman JM, Sopky BJ, Godges JJ, Flynn TW. American Physical Therapy Association. Neck pain: clinical practice guidelines linked to the international classification of functioning, disability, and health from the orthopaedic section of the American physical therapy association. J Orthop Sports Phys Ther. 2008; 38: A1–A34. PubMed Google Scholar
- Fernandes L, Hagen KB, Bijlsma JW, Andreassen O, Christensen P, Conaghan PG, Doherty M, Geenen R, Hammond A, Kjeken I, Lohmander LS, Lund H, Mallen CD, Nava T, Oliver S, Pavelka K, Pitsillidou I, da Silva JA, de la Torre J, Zanoli G, Vliet Vlieland TP. European League Against Rheumatism (EULAR):. EULAR recommendations for the non-pharmacological core management of hip and knee osteoarthritis. Ann Rheum Dis. 2013; 72(7): 1125– 1135. doi: 10.1136/annrheumdis-2012-202745. DOI Crossref PubMed Google Scholar
- Jordan JL, Holden ME, Mason EEJ, Foster NE. Interventions to improve adherence to exercise for chronic musculoskeletal pain in adults. Cochrane Database Syst Rev. 2010; 1 CD005956. Patients Adherence and Home Exercises Bruno Bonnechère, et al. DOI Crossref PubMed Google Scholar
- Holden MA, Haywood KL, Potia TA, Gee M, McLean S. Recommendations for exercise adherence measures in musculoskeletal settings: a systematic review and consensus meeting (protocol). Syst Rev. 2014; 3:10. doi: 10.1186/2046-4053-3-10. Review. DOI Crossref PubMed Google Scholar
- Ludwig EG, Adams SD. Patient cooperation in a rehabilitation center: assumption of the client role. J Health Soc Behav. 1996; 9: 328-336 PubMed Google Scholar
- Di Fabio RP, Mackey G. Physical therapy outcomes for patients receiving worker's compensation following treatment for herniated lumbar disc and mechanical low back pain syndrome. J Orthop Sports Phys Ther. 1996; 23(3): 180-7. DOI Crossref PubMed Google Scholar
- Taylor AH, May S. Threat and coping appraisal as determinants of compliance with sport injury rehabilitation: an application of Protection Motivation Theory. J Sports Sci. 1996; 14(6): 471-82. DOI Crossref PubMed Google Scholar
- Almekinders LC, Almekinders SV. Outcome in treatment of chronic overuse sports injuries: a retrospective study. J Orthop Sports Phys Ther. 1994 Mar;19(3):157-61. DOI Crossref PubMed Google Scholar
- Van Gool CH, Penninx BW, Kempen GI, Rejeski WJ, Miller GD, van Eijk JT, Pahor M, Messier SP. Effects of exercise adherence on physical function among overweight older adults with knee osteoarthritis. Arthritis Rheum. 2005; 53(1): 24-32. DOI Crossref PubMed Google Scholar
- Sluijs EM, Kok GJ, van der Zee J. Correlates of exercise compliance in physical therapy. Phys Ther. 1993; 73(11): 771-82; discussion 783-6. DOI Crossref PubMed Google Scholar
- Ice R. Long-term compliance. Phys Ther. 1985;65(2):1832-9. DOI Crossref PubMed Google Scholar
- Barton CJ, Lack S, Hemmings S, Tufail S, Morrissey D. The 'Best Practice Guide to Conservative Management of Patellofemoral Pain': incorporating level 1 evidence with expert clinical reasoning. Br J Sports Med. 2015 Feb 25. pii: bjsports-2014-093637. DOI Crossref PubMed Google Scholar
- Celinder D, Peoples H. Stroke patients' experiences with Wii Sports® during inpatient rehabilitation. Scand J Occup Ther. 2012; 19(5): 457-63. DOI Crossref PubMed Google Scholar
- Jannink MJ, van der Wilden GJ, Navis DW, Visser G, Gussinklo J, Ijzerman M. A low-cost video game applied for training of upper extremity function in children with cerebral palsy: a pilot study. Cyberpsychol Behav. 2008; 11(1): 27-32. DOI Crossref PubMed Google Scholar
- Chan TC, Chan F, Shea YF, Lin OY, Luk JK, Chan FH. Interactive virtual reality Wii in geriatric day hospital: a study to assess its feasibility, acceptability and efficacy. Geriatr Gerontol Int. 2012; 12(4): 714-21. DOI Crossref PubMed Google Scholar
- Aitken D, Buchbinder R, Jones G, Winzenberg T. Interventions to improve adherence to exercise for chronic musculoskeletal pain in adults. Aust Fam Physician. 2015; 44(1): 39-42. PubMed Google Scholar
Read the full text
Open the PDF here
Loading the PDF…
If the PDF does not show here, use the download button above.
How to cite this article
Bonnechere B, Jansen B, Omelina L, Jan SVS. Do Patients Perform Their Exercises at Home and why (not)? A Survey on Patient Habits during Rehabilitation Exercises. Ulutas Med J. 2016;2(1):41-46. doi:10.5455/umj.20160210060312
Bonnechere, B., Jansen, B., Omelina, L., & Jan, S. V. S. (2016). Do Patients Perform Their Exercises at Home and why (not)? A Survey on Patient Habits during Rehabilitation Exercises. The Ulutas Medical Journal, 2(1), 41–46. https://doi.org/10.5455/umj.20160210060312
Bonnechere, B. et al. (2016) 'Do Patients Perform Their Exercises at Home and why (not)? A Survey on Patient Habits during Rehabilitation Exercises', The Ulutas Medical Journal, 2(1), pp. 41–46. doi: 10.5455/umj.20160210060312.