The Ulutas Medical Journal · ISSN 2149-0430 (print), 2149-388X (online) · https://www.ulutasmedicaljournal.com/?mno=166235
Original Article · Open access
Comparative Outcomes of Surgical Treatments for Primary Stress Urinary Incontinence in Women: A Retrospective Cohort Study
Abstract
- Introduction
- The study evaluates the outcomes of different surgical techniques, including Tension-free Vaginal Tape (TVT), Trans-Obturator Tape (TOT), Burch Colpopexy (BC), and Anterior Vaginal Wall Prolapse Repair (APR), in treating primary stress urinary incontinence (SUI) in women.
- Materials and Methods
- A retrospective cohort study was conducted in a tertiary care center, comprising 62 women diagnosed with primary SUI who underwent one of the aforementioned surgical procedures. Demographic and clinical variables were analyzed, including age, BMI, menopausal status, reproductive history, incontinence types, anticholinergic use, and preoperative assessments.
- Results
- No differences were found in age (p=0.227), weight (p=0.943), height (p=0.333), and BMI (p=0.642) among the four treatment groups. The distribution of menopausal patients and reproductive history variables did not differ among the groups. Postoperative anticholinergic prescription rates (p=0.769) and duration of use (p=0.531) were not different across the groups. The majority of patients in the TVT, TOT, and BC groups had a grade 2 cystocele (p=0.065). The BC group had 100% grade 1 rectocele, which was not significant compared to other groups (p=0.126).
- Conclusion
- Our results showed no potential difference in comparable outcomes among TVT, TOT, BC, and APR for the surgical treatment of primary SUI.
Keywords
Full text
Introduction
Stress urinary incontinence (SUI) is defined as the involuntary loss of urine during physical exertion or activity that increase intraabdominal pressure, such as coughing, sneezing, or lifting (1). It is a highly prevalent condition in women, affecting up to 35% of the female population (2). Despite its widespread occurrence, SUI remains underdiagnosed and undertreated, causing impairments in quality of life, self-esteem, and social interactions (3).
Several factors contribute to the development of SUI in women, including aging, obesity, parity, and hormonal changes (4). The condition arises from a complex interplay of anatomical, neurological, and hormonal factors that weaken the pelvic floor and urethral support structure (5). Conservative approaches, including lifestyle modifications, pelvic floor muscle training, and behavioural therapies, are usually the first-line treatment options (6). However, surgical interventions may be necessary for cases of moderate-to-severe SUI unresponsive to conservative measures (7). Among the surgical techniques for SUI, transobturator tape (TOT), tension-free vaginal tape (TVT), Burch Colpopexy (BC) and Repair of Anterior Vaginal Wall Prolapse (ARP) are widely used (8). These procedures aim to reinforce the weakened pelvic support structures and restore the anatomical and functional integrity of the urinary continence system (9). While each of these approaches has its merits, the selection of the most suitable technique depends on patient factors, surgeon experience, and the specific clinical context.
Comparative studies on the outcomes of these surgical techniques for SUI are sparse and limited in scope. Therefore, this study aims to assess and compare the outcomes of TOT, TVT, BC and ARP in SUI.
Materials and Methods
Study Design
We conducted a retrospective cohort study using data from 62 adult women who had primary SUI at a single tertiary care centre. We compared demographic and clinical characteristics among four groups of patients who underwent various surgical treatments for pelvic organ prolapse or urinary incontinence, including Tension-free Vaginal Tape (TVT), Trans-Obturator Tape (TOT), Burch Colpopexy (BC), and Anterior Vaginal Wall Prolapse Repair (APR). Included were adult women aged 18 years or older, with a primary diagnosis of SUI who received one of the 3 surgical treatments. Exclusion criteria were previous surgery for SUI, concurrent pelvic organ prolapse surgery, neurogenic bladder,insufficient medical records and unwillingness to join to study.
Ethical Statements
This study was conducted in accordance with the Declaration of Helsinki and its later amendments. The research protocol was reviewed and approved by the Institutional Review Board (IRB) of the tertiary care centre where the study was conducted.
Data Collection
For the collection, we systematically reviewed medical records and extracted relevant patient information. We collected demographic information, including age, weight, height, and body mass index (BMI). The reproductive history parameters comprised menopausal status, age at menarche, gravidity, parity, difficult urination, caesarean section, abortion, and total abdominal hysterectomy + bilateral Salpingooferectomy (TAH+BSO). We gathered information on the patient's medical history, such as enuresis status and thyroid hormone levels, as well as incontinence characteristics, including the type of incontinence. The use of anticholinergic medications and the duration of use were recorded. In addition, we collected information on the preoperative assessment, including daily pad count and the presence of cystocele and rectocele.
Surgical Techniques
Transobturator tape (TOT): A synthetic mesh tape was placed under the mid-urethra via the transobturator route from the thigh. Tension-free vaginal tape (TVT): A similar synthetic mesh tape was placed under the mid-urethra using a retropubic approach. Burch Colpopexy (BC): This procedure involved partial closure of the vaginal canal using the LeFort technique, which preserves the uterus and is generally reserved for older women.
Statistical Analysis
All statistical analyses were performed using Statistical Package for the Social Sciences (SPSS) version 26.0. Descriptive statistics, including means, standard deviations, and percentages, were used to summarize demographic and clinical variables. The Shapiro-Wilk test was used to assess normality of the distribution. For continuous variables, the student’s t-test was used to compare means between two groups if the data were normally distributed; otherwise, the Mann-Whitney U was used. For categorical variables, the chi-square test was used, or the Fisher's exact test was employed when expected cell counts were less than 5. Analysis of variance (ANOVA) or the Kruskal-Wallis test was used to compare means among the three surgery groups (TOT, TVT, BC and ARP), followed by post-hoc tests to evaluate pairwise comparisons. For all analyses, a p-value of less than 0.05 was considered statistically significant.
Results
Our findings revealed no differences in age, weight, height, and BMI among the four groups (p-values 0.227, 0.943, 0.333, and 0.642, respectively). Furthermore, the distribution of menopausal patients, those with a history of difficult birth, caesarean section, abortion, TAH- BSO surgery, and infection did not significantly differ among the four groups. The prevalence of patients who had experienced stress, Stress+Urge, and urge incontinence types also showed no significant differences among the groups (Table-1).
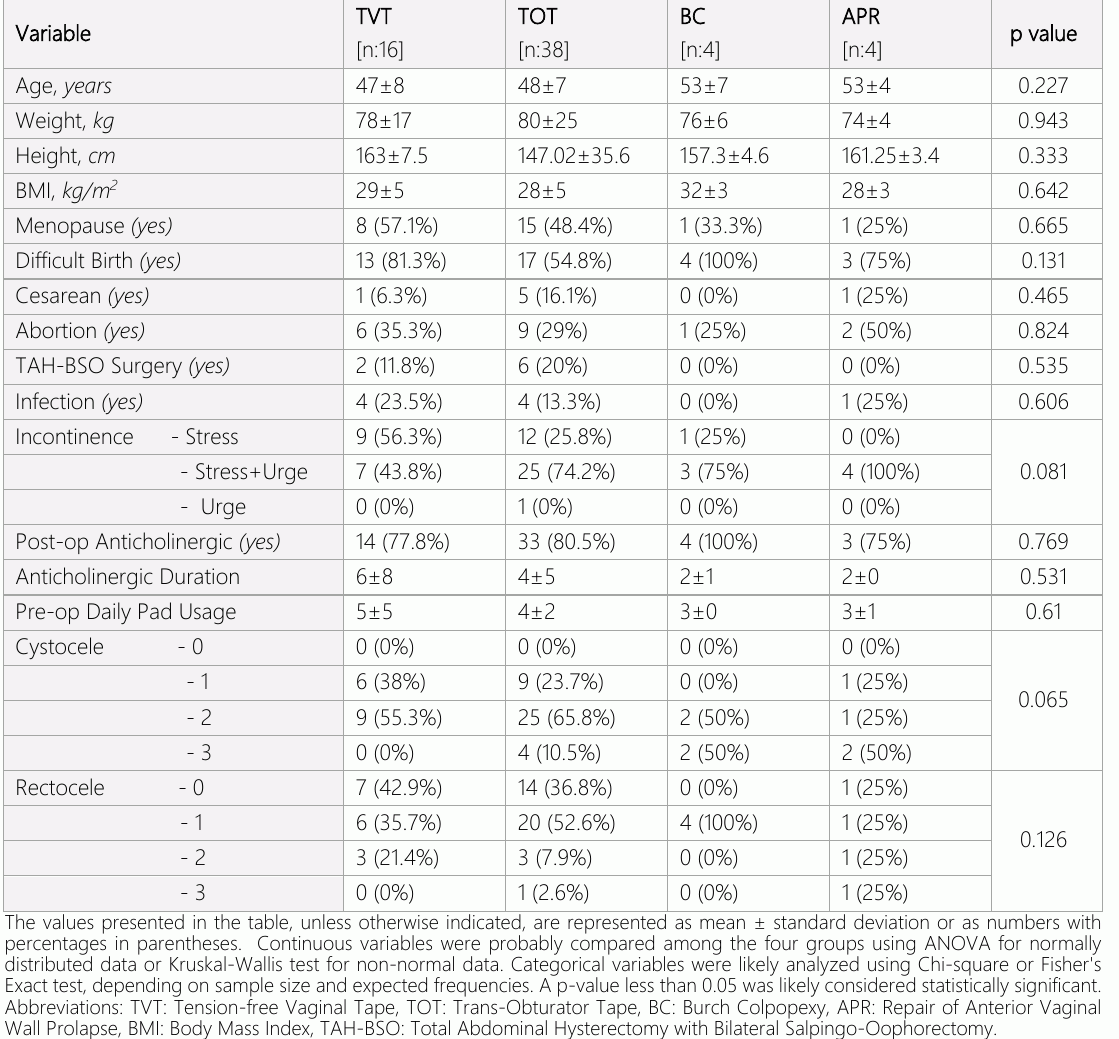
In the TVT group, 14 patients (77.8%) were prescribed postoperative anticholinergic care, compared to 33 patients (80.5%) in the TOT group, 4 patients (100%) in the BC group, and 3 patients (75%) in the APR group. However, the differences were not significant (p=0.769). Similarly, the mean duration of anticholinergic use showed no differences across the groups (p=0.531). Preoperative daily pad usage was similar across the four groups, with no statistically significant differences (p=0.61).
In terms of cystocele grading, no differences were found among the groups (p=0.065). The majority of the patients had a grade 2 cystocele in the TVT, TOT, and BC groups. In the rectocele grading, although the BC group showed 100% grade 1 rectocele, this difference was not statistically significant compared to the other groups (p=0.126).
Discussion
Our retrospective cohort study evaluated various surgical treatments for primary stress SUI in adult women, including TOT, TVT, BC, and APR. Our findings revealed no differences in demographic and clinical characteristics, including age, weight, BMI, menopausal status, reproductive history, and incontinence types, among the four treatment groups. These results provide a balanced foundation for assessing the outcomes of different surgical approaches for patients with SUI.
Stress urinary incontinence is a common condition affecting many women, caused by loss of support of the urethra and different procedures are considered effective in all types of SUI surgeries in the past decades (10–12). The study of Huang et al. (13), noticed the effectiveness of the repeat sling appeared to depend on adequate post-operative urethral mobility and urethral closure pressure. Regarding the type of procedure, various studies reported that retropubic suburethral procedures have a better cure rate than transobturator procedures in SUI (14, 15). Recent studies have revealed that the success rate of repeated suburethral sling procedures was better for slings positioned at the proximal urethra (4, 16, 17). Urodynamic stress incontinence is more likely observed in women with a greater sling-pubis gap, and sling location should be close to the symphysis pubic to reduce the length of the urethral funnelling (18). According to Lo et al. (15), mid urethral slings surgery including TOT and TVT, is safe for the young and aging patients with USI and demonstrated improvement in its outcomes, but objective and subjective cure rates decrease with age.
Our findings revealed no differences among the groups in terms of age, weight, height, BMI, menopausal status, history of difficult birth, cesarean section, abortion, TAH-BSO surgery, infection, or incontinence types. Postoperative anticholinergic medication uses and duration of use, as well as preoperative daily pad usage, were similar across the groups. Furthermore, there were no differences in cystocele grading among the groups, with the majority of patients having a grade 2 cystocele in the TVT, TOT, and BC groups. Although the BC group showed 100% grade 1 rectocele, this difference was not significant compared to the other groups.
Our study has several limitations that should be acknowledged. First, the relatively small sample size of each treatment group might limit the generalizability of the results. Second, we did not account for potential confounding factors such as the surgeon's experience, patient compliance, and postoperative care, which could affect treatment outcomes. Additionally, the follow-up period was not uniform across all participants, which may introduce potential bias in the assessment of outcomes. Lastly, the lack of a standardized outcome measure to assess treatment success limits the comparison of results with other studies. Despite these limitations, our study has several strengths that merit attention. We included a diverse patient population with various clinical presentations of SUI, which increases the external validity of the findings. We also provided a comprehensive assessment of patient demographics, medical history, and incontinence types, which offers a holistic view of the patient characteristics associated with SUI. Furthermore, we performed rigorous statistical analyses, taking into account potential confounders and differences among the groups, to provide a robust evaluation of the outcomes. Finally, our study directly compared multiple surgical treatment options for primary SUI, which can contribute to the development of personalized treatment strategies for patients with SUI.
Conclusion
Our results indicate that demographic and clinical characteristics, including age, weight, height, BMI, menopause status, history of difficult birth, caesarean section, abortion, TAH- BSO surgery, infection, incontinence type, postoperative anticholinergic use and duration, preoperative daily pad usage, and cystocele and rectocele grades, were similar among patients undergoing TVT, TOT, BC, or APR surgical interventions for urinary incontinence. Therefore, the choice of surgical approach can be tailored to individual patient needs, taking into consideration factors such as expertise, preference, and comorbidity. Further research with larger sample sizes and longer follow-up periods is needed to better assess the long-term outcomes and potential advantages of each surgical approach.
Declarations
- Author contributions (CRediT)
- All authors contributed equally to all 14 CRediT roles (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- Funding
-
Funding information was not reported in the published version of this article.
- Conflicts of interest
- The author declares no conflict for the present research article.
- Ethics approval
- Ethical Statements This study was conducted in accordance with the Declaration of Helsinki and its later amendments.
- Data availability
- A data availability statement was not reported in the published version of this article.
References (18)
17 of 18 references are linked to their DOI.
- Trowbridge ER, Hoover EF. Evaluation and Treatment of Urinary Incontinence in Women. Gastroenterol Clin North Am. 2022;51(1):157-75. DOI Crossref PubMed Google Scholar
- Sazonova NA, Kiseleva MG, Gadzhieva ZK, Gvozdev MY. [Urinary incontinence in women and its impact on quality of life]. Urologiia. 2022(2):136-9. DOI Crossref PubMed Google Scholar
- Tunn R, Baessler K, Knüpfer S, Hampel C. Urinary Incontinence and Pelvic Organ Prolapse in Women. Dtsch Arztebl Int. 2023;120(5):71-80. DOI Crossref PubMed Google Scholar
- Călinescu BC, Neacșu A, Martiniuc AE, Dumitrescu D, Stănică CD, Roșu GA, et al. Surgical Treatments for Women with Stress Urinary Incontinence: A Systematic Review. Life (Basel). 2023;13(7). DOI Crossref PubMed Google Scholar
- Frigerio M, Barba M, Cola A, Braga A, Celardo A, Munno GM, et al. Quality of Life, Psychological Wellbeing, and Sexuality in Women with Urinary Incontinence-Where Are We Now: A Narrative Review. Medicina (Kaunas). 2022;58(4). DOI Crossref PubMed Google Scholar
- Klapper-Goldstein H, Tamam S, Sade S, Weintraub AY. A systematic review of stem cell therapy treatment for women suffering from stress urinary incontinence. Int J Gynaecol Obstet. 2022;157(1):19-30. DOI Crossref PubMed Google Scholar
- Pivazyan L, Kasyan G, Grigoryan B, Pushkar D. Effectiveness and safety of bulking agents versus surgical methods in women with stress urinary incontinence: a systematic review and meta-analysis. Int Urogynecol J. 2022;33(4):777-87. DOI Crossref PubMed Google Scholar
- Ross S, Robert M, Lier D, Eliasziw M, Jacobs P. Surgical management of stress urinary incontinence in women: safety, effectiveness and cost-utility of trans-obturator tape (TOT) versus tension-free vaginal tape (TVT) five years after a randomized surgical trial. BMC Womens Health. 2011;11:34. DOI Crossref PubMed Google Scholar
- Kim HG, Park HK, Paick SH, Choi WS. Comparison of Effectiveness between Tension -Free Vaginal Tape (TVT) and Trans-Obturator Tape (TOT) in Patients with Stress Urinary Incontinence and Intrinsic Sphincter Deficiency. PLoS One. 2016;11(5):e0156306. DOI Crossref PubMed Google Scholar
- Song CQ, Zhu YP, Han BM, Xia SJ. [Overview of risk factors for stress urinary incontinence and strategies in its prevention and treatment]. Zhonghua Yi Xue Za Zhi. 2022;102(48):3811-4. PubMed Google Scholar
- Bodmer NS, Wirth C, Birkhäuser V, Sartori AM, Leitner L, Averbeck MA, et al. Randomised Controlled Trials Assessing the Clinical Value of Urodynamic Studies: A Systematic Review and Meta-analysis. Eur Urol Open Sci. 2022;44:131-41. DOI Crossref PubMed Google Scholar
- Krause EL, Hattersley AM, Abbinante-Nissen JM, Gutshall D, Woeller KE. Support of adult urinary incontinence products: recommendations to assure safety and regulatory compliance through application of a risk assessment framework. Front Reprod Health. 2023;5:1175627. DOI Crossref PubMed Google Scholar
- Huang Y, Chen Z, Shen B, Shao Y, Gao J, Zhou Y, et al. Management and Follow-Up Practices of Women With Recurrent Stress Urinary Incontinence Following Transobturator Mid-urethral Synthetic Sling Procedure: A 6-Year Retrospective Monocentric University-Based Study. Front Surg. 2021;8:710594. DOI Crossref PubMed Google Scholar
- Ford AA, Ogah JA. Retropubic or transobturator mid-urethral slings for intrinsic sphincter deficiency-related stress 157 77 Primary Stress Urinary Incontinence in Women Kazım Doğan urinary incontinence in women: a systematic review and meta-analysis. Int Urogynecol J. 2016;27(1):19-28. DOI Crossref PubMed Google Scholar
- Lo TS, Shailaja N, Tan YL, Wu MP, Chua S, Roy KW. Outcomes and failure risks in mid -urethral sling insertion in elderly and old age with urodynamic stress incontinence. Int Urogynecol J. 2020;31(4):717-26. DOI Crossref PubMed Google Scholar
- Sarrazin C, Baron M, Thuillier C, Ruffion A, Perrouin-Verbe MA, Fiard G. Synthetic mid-urethral slings for the treatment of stress urinary incontinence in women with neurogenic lower urinary tract dysfunction: a systematic review. Int Urogynecol J. 2022;33(4):767-76. DOI Crossref PubMed Google Scholar
- Zheng Y, Rovner E. Update on Urethral Bulking for Stress Urinary Incontinence in Women. Curr Urol Rep. 2022;23(10):203-9. DOI Crossref PubMed Google Scholar
- Patel T, Sugandh F, Bai S, Varrassi G, Devi A, Khatri M, et al. Single Incision Mini-Sling Versus Mid-Urethral Sling (Transobturator/Retropubic) in Females with Stress Urinary Incontinence: A Systematic Review and Meta-Analysis. Cureus. 2023;15(4):e37773. DOI Crossref PubMed Google Scholar
Respond to this article
Comments on a published article are welcome as a Letter to the Editor.
Get an e-mail when new articles in your fields are published
Questions to the authors
Questions are moderated: an editor approves each question, the authors answer, and an editor approves the answer before both appear here.
No answered questions yet.
Ask the authors a question
Discussion
Comments are moderated: they appear after the writer confirms the e-mail address and an editor approves them. Each comment carries a conflict-of-interest statement.
No comments yet.
Write a comment
Read the full text
Open the PDF here
Loading the PDF…
If the PDF does not show here, use the download button above.
How to cite this article
Dogan K. Comparative Outcomes of Surgical Treatments for Primary Stress Urinary Incontinence in Women: A Retrospective Cohort Study. Ulutas Med J. 2023;9(3):152-157. doi:10.5455/umj.20230821091835
Dogan, K. (2023). Comparative Outcomes of Surgical Treatments for Primary Stress Urinary Incontinence in Women: A Retrospective Cohort Study. The Ulutas Medical Journal, 9(3), 152–157. https://doi.org/10.5455/umj.20230821091835
Dogan, K. (2023) 'Comparative Outcomes of Surgical Treatments for Primary Stress Urinary Incontinence in Women: A Retrospective Cohort Study', The Ulutas Medical Journal, 9(3), pp. 152–157. doi: 10.5455/umj.20230821091835.